Fat dissolving injections are a category of non-surgical cosmetic treatment used to reduce localised deposits of subcutaneous fat. The most established active substance used in this context is deoxycholic acid — a bile acid that disrupts the membrane of fat cells, causing them to break down and be cleared from the body through natural metabolic processes. In Australia, these treatments are most commonly applied to the area beneath the chin (submental fat), though they are also used in other areas with localised fat deposits.
Quick answer: Fat dissolving injections use deoxycholic acid or similar lipolytic substances to permanently destroy fat cells in targeted areas. The most common treatment area in Australia is under the chin (submental fat, sometimes called a double chin). Destroyed fat cells do not regenerate — however, remaining fat cells in the area can still enlarge with weight gain. Multiple sessions are typically required. Treatment must be performed by a qualified medical practitioner under a valid prescription in Australia.
What substances are used in fat dissolving injections?
The primary substance used in evidence-based fat dissolving treatment is deoxycholic acid. In Australia, the most widely used TGA-registered product for submental fat reduction is Belkyra (known as Kybella in the United States), which contains synthetic deoxycholic acid at a concentration of 10mg/mL.
Deoxycholic acid is a secondary bile acid that occurs naturally in the body, where it assists with the emulsification and absorption of dietary fat in the digestive system. When introduced into subcutaneous fat tissue, it disrupts the phospholipid membrane of fat cells (adipocytes), causing cytolysis — cell destruction. The released cellular contents are then cleared by the body’s immune and lymphatic systems over the following weeks.
Other substances used in fat-dissolving treatments globally include phosphatidylcholine (PC), sodium deoxycholate combinations, and various proprietary lipolytic blends. The evidence base for these alternatives is less robust than for deoxycholic acid, and their regulatory status in Australia varies. When considering treatment, it is important to confirm the specific product being used and its TGA registration status.
How do fat dissolving injections work — the mechanism
Understanding the mechanism of fat dissolving injections helps set realistic expectations about the treatment timeline and what to anticipate during recovery.
The process occurs in several phases:
- Injection and initial cell disruption: Deoxycholic acid is introduced into the subcutaneous fat layer via multiple small injections distributed across the treatment area. The acid disrupts fat cell membranes immediately on contact.
- Inflammatory response: The destruction of fat cells triggers a localised inflammatory response. This is expected and is the reason for the significant swelling, firmness, and tenderness that typically occur in the days following treatment. Swelling can be pronounced — particularly under the chin — and may persist for one to four weeks.
- Macrophage clearance: The body’s macrophages (immune cells) migrate to the treatment area and begin clearing the debris from destroyed fat cells. This process, combined with lymphatic drainage, gradually removes the destroyed cellular material over four to eight weeks.
- Collagen remodelling: As the inflammatory phase resolves, the treatment area undergoes some degree of collagen remodelling, contributing to skin tightening in the treated zone.
- Final result: The full result is typically visible at six to eight weeks after each session. Because fat cells are permanently destroyed, the result in the treated area is maintained provided overall body weight remains stable.
A landmark phase III clinical trial published in the JAMA Dermatology journal found that patients treated with deoxycholic acid for submental fat experienced statistically significant reductions in submental fat volume compared to placebo, with improvements in patient-reported satisfaction and clinician assessment of chin profile.
What areas can fat dissolving injections treat?
The most common treatment area in Australia, and the area with the strongest clinical evidence, is submental fat — the fat pad beneath the chin that creates the appearance of a double chin. This is also the indication for which Belkyra (deoxycholic acid) holds TGA registration.
Treatment is also used off-label for other areas with discrete fat deposits, though the evidence base is less robust for these locations:
| Treatment area | Clinical description | Evidence status in Australia |
|---|---|---|
| Submental (under chin) | Reduction of double chin fat pad | TGA-registered indication |
| Jowls | Reduction of jowl fat contributing to lower face heaviness | Off-label, clinical evidence available |
| Bra strap fat | Reduction of fat pad at the lateral chest/upper back | Off-label |
| Axillary fat (underarm) | Reduction of discrete underarm fat | Off-label |
| Knee fat | Reduction of fat around the knee | Off-label, limited evidence |
| Small abdominal deposits | Not a body contouring treatment — unsuitable for large areas | Limited evidence; not first-line |
It is important to note that fat dissolving injections are a treatment for discrete, localised fat deposits — not a weight loss intervention or a treatment for generalised body fat. Suitable candidates have a specific, contained fat pad that is not responsive to dietary and lifestyle change.
For a detailed overview of the double chin treatment approach specifically, the guide to double chin fat removal is the most comprehensive resource available. The double chin treatment suitability guide covers how to determine whether this approach is appropriate for a given individual.
Are fat dissolving injections permanent?
The fat cells destroyed by deoxycholic acid treatment do not regenerate. In this sense, the destruction of those specific cells is permanent. However, two important caveats apply:
First, not all fat cells in the treatment area are necessarily destroyed in a single session. Multiple sessions — typically two to four for the submental area — are required to achieve clinically meaningful results. Each session destroys a proportion of the fat cells in the treatment zone, with the effect compounding across sessions.
Second, the remaining fat cells in the treatment area — and fat cells elsewhere in the body — retain the capacity to enlarge if overall body weight increases. Fat dissolving treatment does not prevent future fat accumulation; it reduces the number of fat cells present at the time of treatment. Patients who gain significant weight after treatment may notice some return of fat in the treated area.
This is an important distinction from surgical fat removal procedures such as liposuction, which can remove a higher proportion of fat cells in a single session. For a comparison of approaches, the fat dissolving vs other treatments guide provides an objective breakdown of the clinical differences.
How many sessions are needed?
The number of sessions required depends on the volume of fat in the treatment area, the individual’s response to treatment, and the desired outcome. For submental fat, most clinical guidelines suggest two to four sessions spaced four to six weeks apart, though some patients with larger fat deposits may require more.
Each session is assessed at the four to six-week mark before the decision to proceed with another session is made. This allows the practitioner and patient to evaluate how much reduction has occurred and whether further treatment is warranted.
Because results accumulate across sessions, it is important not to assess the final outcome too early. The most significant reduction in submental fat volume typically becomes apparent after the second or third session, once the inflammatory response from each treatment has fully resolved.
What does recovery look like?
Recovery from fat dissolving treatment — particularly for submental fat — is more significant than many patients expect, and managing expectations about the post-treatment period is an important part of the pre-treatment consultation.
Typical post-treatment experience in the submental area includes:
- Days 1–3: Significant swelling, firmness, and tenderness under the chin. The area may feel numb or have a burning sensation. This is a direct result of the inflammatory process and is expected.
- Days 4–14: Swelling begins to reduce, though the area may remain noticeably firm and slightly tender. Bruising may be present.
- Weeks 2–4: Firmness gradually softens as the inflammatory phase resolves. The area begins to look and feel more normal, though the fat reduction is not yet fully apparent.
- Weeks 6–8: Fat reduction becomes visible. This is the appropriate point to assess results and plan subsequent sessions if required.
For a more detailed breakdown of the recovery process, the aftercare guide for fat dissolving treatments explains what to expect at each stage and how to manage the recovery period. The mechanism behind the swelling and inflammation is explained in more detail in the guide on how under-chin fat dissolving injections work.
What are the risks and side effects?
Fat dissolving treatment has a well-characterised side effect profile. Most effects are expected consequences of the inflammatory mechanism rather than complications in the traditional sense.
Expected and common effects include swelling (often significant in the submental area), bruising, tenderness, firmness or lumpiness in the treated area, and temporary numbness. These typically resolve over two to four weeks.
Less common but clinically relevant risks include:
- Marginal mandibular nerve injury: The marginal mandibular branch of the facial nerve runs along the lower jaw. If deoxycholic acid is placed too close to this nerve, temporary weakness of the lip depressors may occur. This is almost always temporary and resolves without intervention, but proper anatomical knowledge and correct injection placement are essential to minimising this risk.
- Skin irregularity: Uneven fat reduction can result in an irregular surface contour. This is more likely when treatment is performed without a consistent injection pattern or when product is placed outside the target fat layer.
- Over-treatment: Removing too much fat in a single area — particularly under the chin — can result in excess skin laxity. Careful assessment of skin quality prior to treatment is an important part of the suitability evaluation.
- Alopecia: Hair loss in the treatment area has been reported, though it is rare and typically temporary.
The clinical trial programme supporting Belkyra’s TGA approval included safety monitoring across a large patient cohort. The most frequently reported adverse events were consistent with the expected inflammatory mechanism — swelling, bruising, pain, numbness, and hardness — with serious adverse events occurring at low rates.
Who is suitable for fat dissolving treatment?
A careful suitability assessment is essential before fat dissolving treatment. Not everyone with a double chin or unwanted fat deposit is a good candidate for this approach.
Ideal candidates have:
- A discrete, localised subcutaneous fat deposit in the treatment area
- Relatively good skin elasticity — sufficient to contract after fat reduction without leaving excess loose skin
- A body weight that is broadly stable, or manageable — significant ongoing weight fluctuation is likely to compromise results
- Realistic expectations about the number of sessions required and the timeline to final results
Fat dissolving treatment is generally not appropriate for people whose double chin or jowling is primarily caused by skin laxity rather than fat. In these cases, the fat may be minimal, and dissolving it further may worsen the appearance by removing structural support without the benefit of skin contraction.
People with active skin conditions, infections, or anatomical considerations that place nerves or other structures at elevated risk in the treatment area require careful assessment. Pregnancy and breastfeeding are contraindications to treatment.
The question of what causes a double chin — and whether it is primarily fat, skin, or structural — is explored in detail in the double chin causes guide. Understanding the cause is the first step in determining whether fat dissolving treatment, an alternative approach, or a combination is most appropriate.
Frequently asked questions about fat dissolving injections
How long do fat dissolving injections take to work?
Results develop gradually as the inflammatory process resolves and the body clears the destroyed fat cells. The most meaningful assessment of results from any single session should be made at six to eight weeks. For most people, the clearest visible reduction becomes apparent after the second or third session.
Do fat dissolving injections hurt?
The treatment itself is uncomfortable — multiple small injections are placed across the treatment area, and deoxycholic acid causes a brief burning sensation on contact. Most practitioners use topical anaesthetic cream and/or ice to manage discomfort during the procedure. The post-treatment period — particularly the first 72 hours — is when most patients find discomfort most significant, as swelling and tenderness develop.
Can fat dissolving injections be used on the body?
Fat dissolving injections are used off-label for various body areas including jowls, bra strap fat, axillary fat, and areas around the knees. The evidence base for body applications is less robust than for submental fat, and the anatomy and recovery experience differ by area. The TGA-registered indication for Belkyra is specific to submental fat.
How much swelling should I expect under the chin?
Submental swelling after fat dissolving treatment can be quite pronounced — some patients experience swelling that temporarily makes the area appear larger than before treatment. This is a normal consequence of the inflammatory mechanism and is not a sign that the treatment has gone wrong. Swelling is typically most significant in the first three to five days and gradually reduces over two to four weeks.
Are fat dissolving injections the same as lipolysis?
Lipolysis is the general term for any process that breaks down fat. Fat dissolving injections using deoxycholic acid are a form of chemical lipolysis — as distinct from other forms such as laser lipolysis (e.g. Sculpsure) or cryolipolysis (e.g. CoolSculpting). Each approach has different mechanisms, evidence profiles, costs, and suitability criteria.
Who should not have fat dissolving injections?
People who are pregnant or breastfeeding should not have this treatment. People with active infections, skin conditions, or bleeding disorders require careful assessment. Those whose unwanted fat is primarily loose skin rather than subcutaneous fat are generally not suitable candidates. A thorough pre-treatment consultation with a qualified medical practitioner is the only way to establish individual suitability.
References
- Therapeutic Goods Administration. (2023). Australian Public Assessment Report: Deoxycholic acid (Belkyra). Australian Government Department of Health and Aged Care. https://www.tga.gov.au/
- Jones, D.H., et al. (2016). Efficacy and safety of ATX-101 (deoxycholic acid injection) for the reduction of submental fat: results from a phase III, randomised, placebo-controlled trial. JAMA Dermatology, 152(4), 383–391.
- Dayan, S.H., et al. (2016). ATX-101 (deoxycholic acid injection) for reduction of submental fat: 24-month follow-up results. Dermatologic Surgery, 42(Suppl 1), S225–S229.
Dermal filler is a broad term for injectable substances used to add volume, reshape facial structures, and soften the appearance of lines and hollows. In clinical practice, the term almost exclusively refers to products based on hyaluronic acid — a sugar molecule naturally present in the body’s connective tissue and skin. When placed precisely into specific facial layers, these products can restore volume, improve contour, and address changes associated with facial ageing or structural asymmetry.
Quick answer: Dermal filler refers primarily to hyaluronic acid-based products used to add volume, shape, and definition to facial structures including the lips, cheeks, chin, jawline, tear troughs, and nose. Results are temporary — typically lasting six to eighteen months depending on the area — and the effects can be dissolved with an enzyme called hyaluronidase if needed. Treatment must be performed by a qualified medical practitioner under a valid prescription in Australia.
What is dermal filler made from?
The vast majority of dermal filler products used in Australian clinical practice contain cross-linked hyaluronic acid (HA). Hyaluronic acid is a naturally occurring glycosaminoglycan — a long-chain sugar molecule found in the skin, joints, and connective tissue throughout the body. It has a strong affinity for water, which is why it creates a volumising and hydrating effect when placed in tissue.
The hyaluronic acid used in dermal fillers is biosynthetically produced rather than derived from animal sources. It is then cross-linked — chemically bonded into a gel structure — to slow down the natural enzymatic breakdown that would otherwise cause it to dissolve rapidly. The degree of cross-linking, and the concentration of hyaluronic acid in the product, determines its physical properties: softer, more lightly cross-linked products suit delicate areas like the lips and tear troughs, while denser, more heavily cross-linked products are used for structural augmentation of areas like the chin and jawline.
Major hyaluronic acid filler brands registered with the TGA in Australia include the Juvederm range (Allergan/AbbVie), the Restylane range (Galderma), Teosyal (Teoxane), and Belotero (Merz). Each product range includes multiple formulations designed for specific anatomical layers and treatment goals.
Non-hyaluronic acid fillers also exist — including calcium hydroxylapatite (Radiesse) and poly-L-lactic acid (Sculptra) — but these are collagen-stimulating agents rather than volumisers in the traditional sense, and they are not reversible. For the purposes of this article, the term “dermal filler” refers to hyaluronic acid-based products unless otherwise specified.
How does dermal filler work?
When placed into the appropriate tissue layer, hyaluronic acid gel integrates with surrounding tissue and attracts water molecules, creating volume and lift. The physical effect depends on where and how deep the product is placed, and which product formulation is selected for the area.
Placement depth varies significantly by treatment area:
- Superficial dermis: Finer products placed here address surface lines and skin texture — used for smokers’ lines, fine perioral lines, and surface hydration applications.
- Deep dermis to subcutaneous fat: The most common placement layer for lip treatment, cheek treatment, and nasolabial fold softening.
- Supraperiosteal (on bone): Used for structural treatments including chin augmentation, jawline definition, and non-surgical rhinoplasty, where the product acts as a scaffold on the underlying bone to reshape visible contour.
After placement, the gel begins to integrate over the following days as it absorbs water and settles. Final results are typically assessed at two weeks. Over subsequent months, the product is gradually broken down by the body’s naturally occurring hyaluronidase enzyme until it is fully metabolised.
What areas can dermal filler treat?
Hyaluronic acid filler is one of the most versatile tools in non-surgical aesthetics, with established applications across the upper, mid, and lower face. The table below summarises common treatment areas and their clinical purposes.
| Treatment area | Clinical purpose | Typical longevity |
|---|---|---|
| Lips | Volume, definition, shape, symmetry correction | 6–12 months |
| Cheeks | Volume restoration, lift, contour enhancement | 12–18 months |
| Tear trough / under eyes | Hollow correction, dark circle reduction | 12–18 months |
| Chin | Projection, shape, vertical height | 12–18 months |
| Jawline | Definition, angularity, shadow improvement | 12–18 months |
| Nose (non-surgical rhinoplasty) | Shape refinement, symmetry, dorsal hump reduction | 9–18 months |
| Nasolabial folds (smile lines) | Fold softening, volume restoration | 9–12 months |
| Marionette lines | Downward fold softening | 9–12 months |
| Temples | Volume restoration, softening of hollow appearance | 12–18 months |
| Upper eyelid | Volume restoration in hollowed upper lid sulcus | 12–18 months |
| Jowls | Softening through lateral face structural support | 12–18 months |
| Forehead | Volume softening of deep static lines | 9–12 months |
| Smokers’ lines | Fine perioral line softening | 6–9 months |
| Non-surgical brow lift | Structural lift through lateral brow support | 12 months |
For a comprehensive overview of how facial structure treatments are planned and sequenced, the facial balancing guide explains the principle of treating the face as an interconnected system rather than addressing individual areas in isolation.
Dermal filler in specific facial areas
Lips
Lip treatment is one of the most common applications of hyaluronic acid filler in Australia. Treatment goals vary considerably between patients — from addressing thin lips to enhancing definition, improving symmetry, or creating a more projected Cupid’s bow. Volume ranges from subtle (0.5ml) to more noticeable (1ml or more), and the appropriate amount depends on existing lip anatomy, the desired outcome, and the patient’s facial proportions.
The non-surgical lip enhancement guide and comprehensive lip filler guide cover the range of approaches in detail, including treatment for thin lips, natural-looking results, and what to expect during recovery.
Under eyes and tear trough
The tear trough is the groove that runs from the inner corner of the eye toward the cheek. Volume loss in this area — which may occur with ageing, or be a structural feature present from early adulthood — creates a hollow shadow that gives the appearance of tiredness or dark circles regardless of sleep quality.
Tear trough treatment is considered technically demanding because the tissue in this area is thin and vascular, and the margin between an excellent and a poor result is narrow. Detailed information on this treatment is available in the under eye tear trough treatment guide.
Cheeks
Cheek volume treatment addresses the mid-face — an area that loses fat and bone density with age, contributing to a flattened appearance, descent of soft tissue, and worsening of nasolabial folds. Strategic placement of filler in the deep fat compartments or on the cheekbone can restore projection and provide a lifting effect on the lower face. The cheek volume treatment guide outlines how this approach works and who is likely to benefit.
Nose (non-surgical rhinoplasty)
Filler placed on the nose can reshape the profile, smooth a dorsal hump, correct asymmetry, or lift a drooping tip without surgery. The non-surgical rhinoplasty complete guide is the most detailed resource available on this approach, covering suitability, what it can and cannot achieve, risks, and the difference between surgical and non-surgical outcomes.
Chin and jawline
Structural treatment of the chin and jawline uses denser, supraperiosteal filler to improve definition and projection. These treatments are frequently planned together as part of a lower face treatment approach. For more on this, the jawline treatment guide and chin contouring guide explain the clinical approach in detail.
How long does dermal filler last?
Longevity varies by treatment area, product formulation, the volume placed, and individual metabolism. As a general guide:
- Lip filler: 6–12 months. Lips are a high-movement area, which accelerates breakdown.
- Mid-face and cheeks: 12–18 months. Deeper placement in lower-movement areas tends to last longer.
- Structural areas (chin, jawline): 12–18 months. Supraperiosteal placement in minimal-movement zones may persist toward the upper end of this range.
- Tear trough: 12–18 months, though individual variation is significant in this area.
- Nasolabial folds and marionette lines: 9–12 months on average.
These are general estimates. Individual metabolism, exercise level, and the specific product used all influence actual longevity. Some patients metabolise filler significantly faster than average.
Can dermal filler be dissolved?
One of the key features of hyaluronic acid filler is that it can be dissolved using hyaluronidase — an enzyme that breaks down hyaluronic acid. This distinguishes HA filler from non-reversible alternatives such as calcium hydroxylapatite or poly-L-lactic acid.
Hyaluronidase is used both as a corrective measure (when a result is unsatisfactory or a complication has occurred) and as a safety intervention in the event of rare but serious complications such as vascular compromise. The availability of a reversal agent is an important safety consideration, and all practitioners administering hyaluronic acid filler should have hyaluronidase immediately available during treatment.
For people considering reversal of existing filler, the guide to reversing lip enhancement explains the dissolution process, what to expect, and when reversal is clinically appropriate.
What are the risks of dermal filler?
Like all invasive procedures, dermal filler treatment carries risks. Most are minor and transient; a small number are serious and require prompt medical management.
Common and expected effects after treatment include bruising, swelling, tenderness, and mild asymmetry in the days following treatment. These typically resolve within one to two weeks.
Clinically significant risks include:
- Vascular occlusion: The most serious risk of filler treatment. Occurs if filler is inadvertently injected into or compresses a blood vessel, cutting off blood supply to the tissue it supplies. Can result in tissue necrosis (skin death) or, in rare cases, blindness if a vessel supplying the retina is affected. This risk underscores the importance of practitioner skill, anatomical knowledge, and access to hyaluronidase.
- Tyndall effect: A bluish discolouration visible through the skin when filler is placed too superficially, most commonly in the tear trough area.
- Nodules or migration: Filler can migrate from its intended location or develop palpable lumps. Risk is higher in high-movement areas and with products placed at incorrect tissue depths.
- Infection: Rare, but possible with any injectable procedure. Delayed nodules appearing weeks to months after treatment may represent a biofilm-associated reaction.
- Granuloma: A delayed foreign body reaction that can occur months to years after treatment.
A 2021 analysis published in Aesthetic Surgery Journal found that vascular complications from facial filler represented the majority of serious adverse events reported in the literature, and that the risk was significantly lower when treatment was performed by practitioners with formal training in vascular anatomy and emergency management protocols.
For detail on risks specific to particular areas, the non-surgical rhinoplasty risks guide and under eye treatment risks guide provide area-specific breakdowns.
Who can administer dermal filler in Australia?
In Australia, hyaluronic acid filler products are Schedule 4 prescription medicines under the Therapeutic Goods Act 1989. They require a valid prescription before administration. The prescribing practitioner must be a registered medical practitioner, and they must conduct a suitability assessment — including a review of medical history, contraindications, and expectations — before treatment proceeds.
Administration may be performed by a medical practitioner, or in some states by a registered nurse or dental practitioner working within an appropriate clinical governance framework and under the oversight of the prescribing practitioner. Requirements vary by state and territory.
The TGA has consistently emphasised that the Schedule 4 classification exists to protect patients by ensuring that treatments are only provided after appropriate clinical assessment.
Frequently asked questions about dermal filler
Is dermal filler painful?
Most hyaluronic acid filler products now include lidocaine — a local anaesthetic — in their formulation, which reduces discomfort during treatment. Topical anaesthetic cream is typically applied beforehand, particularly for sensitive areas such as the lips. Most patients describe the experience as mildly uncomfortable rather than painful, though individual pain tolerance and treatment area affect this.
How soon are dermal filler results visible?
Initial results are visible immediately after treatment, though swelling and bruising in the first few days may distort the appearance. Final results are typically assessed at two weeks, once swelling has resolved and the product has settled into position.
What is the difference between lip filler and dermal filler?
Lip filler is a type of dermal filler — the term simply refers to dermal filler placed specifically in the lips. The product used is typically a softer, more lightly cross-linked hyaluronic acid formulation chosen for the flexibility and movement requirements of the lip area.
Can dermal filler make your face look unnatural?
Results depend heavily on volume selection, product choice, placement technique, and how well the treatment plan accounts for the individual’s facial anatomy and proportions. Overfilling, incorrect placement, or the use of inappropriate products are the most common causes of unnatural-looking results. A concern-based, proportional approach to treatment planning — where the goal is enhancement of natural features rather than maximum volume — is associated with more consistently natural outcomes.
Is there any downtime after dermal filler?
Most people return to normal activities the day after treatment. Bruising, if it occurs, may take up to two weeks to fully resolve. Swelling is typically most prominent in the first 24–72 hours. Strenuous exercise, alcohol, and prolonged sun exposure are generally recommended to be avoided for 24–48 hours post-treatment.
What happens to dermal filler over time?
Hyaluronic acid filler is gradually broken down by the body’s naturally occurring hyaluronidase enzyme. As the product metabolises, volume gradually reduces and the treated area returns toward its pre-treatment appearance. The product does not permanently alter tissue — it is fully biodegradable over time.
References
- Therapeutic Goods Administration. (2023). Prescription medicines: Hyaluronic acid dermal fillers. Australian Government Department of Health and Aged Care. https://www.tga.gov.au/
- DeLorenzi, C. (2021). New high dose pulsed hyaluronidase protocol for hyaluronic acid filler vascular adverse events. Aesthetic Surgery Journal, 37(7), 814–825.
- Humphrey, S., et al. (2021). A practical approach to dermal filler complications. Journal of the American Academy of Dermatology, 84(1), 191–204.
- Nast, A., et al. (2021). European evidence-based consensus recommendations on the use of hyaluronic acid dermal fillers. Journal of the European Academy of Dermatology and Venereology, 35(Suppl 1), 1–21.
Botox is a brand name for a purified form of botulinum toxin type A — a protein that temporarily reduces muscle activity when introduced into targeted muscle groups. In clinical practice, it is used to soften expression-related lines, address excessive sweating, relieve jaw clenching and teeth grinding, and slim the face by reducing the size of the masseter muscle. Results are temporary and typically last between three and six months depending on the area treated and the individual’s response.
Quick answer: Botox is a purified botulinum toxin type A used in medicine and cosmetics to temporarily reduce muscle activity. It is most commonly used to soften forehead lines, frown lines, and crow’s feet, and is also used clinically for conditions including hyperhidrosis (excessive sweating), chronic migraine, and temporomandibular joint (TMJ) disorders. Effects typically begin within two to seven days and last three to six months.
What is botox made from?
Botox is derived from Clostridium botulinum, a bacterium found in nature. The active ingredient — botulinum toxin type A — is extracted, purified, and manufactured in highly controlled conditions to produce a sterile, pharmaceutical-grade protein. In the concentrations used clinically, it is far below the threshold associated with toxicity and has an established safety record spanning several decades of medical use.
Multiple brands of botulinum toxin type A are available in Australia. Botox (manufactured by Allergan, an AbbVie company) is the most widely recognised, but other TGA-registered products include Dysport (abobotulinumtoxinA) and Xeomin (incobotulinumtoxinA). Each product uses a slightly different formulation and unit dosing system, which is why units are not interchangeable between brands.
According to the Therapeutic Goods Administration (TGA), botulinum toxin products are Schedule 4 prescription medicines in Australia. They must be prescribed and administered by a registered medical practitioner or, in some states, a registered nurse or dental practitioner operating within an approved clinical framework.
How does botox work?
Botulinum toxin type A works by blocking the release of acetylcholine — a neurotransmitter that signals muscles to contract. When introduced into a specific muscle, it prevents that muscle from receiving the nerve signal that triggers movement. The result is a temporary, localised reduction in muscle activity in the treated area.
The mechanism unfolds over several days. After treatment, the protein binds to the nerve terminal and begins inhibiting acetylcholine release. Clinical effect typically appears within two to seven days and reaches its peak at around two weeks. Over time, the nerve terminal regenerates new connections, and muscle activity gradually returns — which is why effects are temporary rather than permanent.
This mechanism is well established in peer-reviewed literature. A 2021 review published in the Journal of the American Academy of Dermatology confirmed that botulinum toxin A consistently reduces dynamic wrinkle severity through neuromuscular blockade, with a predictable onset and duration profile across treatment populations.
What is botox used for?
Botulinum toxin type A has both medical and cosmetic applications, and many of its uses are supported by substantial clinical evidence. Below is an overview of established uses.
| Treatment area | Application | Evidence level |
|---|---|---|
| Forehead lines | Softening of horizontal expression lines | Well established |
| Frown lines (glabellar) | Reduction of vertical lines between the brows | Well established |
| Crow’s feet | Softening of lateral eye lines | Well established |
| Brow lifting | Subtle elevation of the brow arch | Well established |
| Masseter reduction | Jaw and facial slimming; TMJ/bruxism management | Well established |
| Hyperhidrosis | Reduction of excessive sweating (underarm, palms, feet) | Well established |
| Chronic migraine | Preventative treatment (31 injection sites per cycle) | TGA-approved indication |
| Platysmal bands (neck) | Softening of vertical neck cords | Established |
| Lip flip | Subtle upper lip eversion | Established |
| Gummy smile | Reduction of excessive upper gum exposure on smiling | Established |
| Calf slimming | Reduction of gastrocnemius muscle bulk | Established |
| Trapezius slimming | Reduction of neck and shoulder bulk; tension relief | Established |
In Australia, the TGA has approved botulinum toxin type A for several specific medical indications. Cosmetic applications — while widely practised — are largely used off-label, which is a standard and legal practice in Australian medicine where clinical evidence supports the use.
How long does botox last?
The duration of effect varies depending on the treatment area, the dose administered, individual metabolism, and whether the person has had prior treatments. In general, most people find that effects persist for three to six months in commonly treated areas.
Several factors influence how long botulinum toxin effects last:
- Treatment area: Areas with smaller, less active muscles — such as around the eyes — often show longer-lasting results than areas with larger, more frequently used muscles like the forehead. Masseter treatments for jaw slimming typically last four to six months per session, with some patients reporting longer intervals after repeated treatments.
- Dose: Higher doses within a clinically appropriate range tend to produce longer duration. Under-dosing for cosmetic reasons can result in reduced longevity.
- Metabolism and activity: People who exercise intensively may metabolise the product more quickly. Higher baseline metabolic rates can also shorten duration.
- Treatment history: Some patients who have received regular treatments over several years report gradually extending intervals between sessions, possibly reflecting cumulative muscle atrophy in targeted areas.
Areas such as the masseter, trapezius, and calves — where treatment goals relate to muscle reduction rather than wrinkle relaxation — often require two or more treatment cycles before the full result is apparent, as muscle bulk reduces gradually with each session.
What are the side effects of botox?
Botulinum toxin type A has a well-characterised safety profile across decades of clinical use. Like any prescription medicine, it carries a risk of side effects — most of which are mild, transient, and localised to the treatment area.
Common side effects include temporary bruising, mild swelling, and localised headache in the hours following treatment. These typically resolve within 24 to 72 hours without intervention.
Less common but clinically relevant side effects include:
- Ptosis (eyelid drooping): Occurs if the product diffuses beyond the intended muscle into the levator palpebrae superioris. Risk is minimised by precise injection placement and appropriate dose selection.
- Brow heaviness or descent: Can occur when treating forehead lines if the frontalis muscle is over-relaxed, particularly in patients with pre-existing brow ptosis.
- Asymmetry: May reflect uneven muscle activity, inconsistent technique, or variable product uptake between sides.
- Dysphagia or dysphonia: Rare, primarily associated with high-dose medical applications (e.g., cervical dystonia treatment) rather than standard cosmetic doses.
Serious adverse events from cosmetic doses are rare. A 2020 systematic review published in the Journal of Cosmetic Dermatology found that serious complications from botulinum toxin use in aesthetic medicine occurred in fewer than 1% of reported cases, with the majority of adverse events being mild and self-limiting.
The TGA publishes adverse event reporting data for prescription medicines including botulinum toxin products through the Database of Adverse Event Notifications (DAEN). People experiencing unexpected symptoms following treatment should report these through their treating practitioner.
Who is a suitable candidate for botox?
Suitability for botulinum toxin treatment depends on the person’s health history, the treatment indication, and an assessment by a qualified medical practitioner. A thorough suitability assessment is a clinical requirement, not a formality.
Botulinum toxin treatment is generally not suitable for:
- People who are pregnant or breastfeeding
- People with known hypersensitivity to botulinum toxin or any product excipients
- People with neuromuscular junction disorders such as myasthenia gravis, Eaton-Lambert syndrome, or amyotrophic lateral sclerosis (ALS)
- People taking certain medications that may potentiate neuromuscular blockade, including aminoglycosides and calcium channel blockers
- People with active infection at the proposed treatment site
People with a history of prior treatments with any botulinum toxin product should disclose this to their treating practitioner, as prior exposure may be clinically relevant when dosing decisions are made.
For cosmetic applications in Australia, the requirement for a valid prescription means that a prescribing consultation must occur before treatment. This is a regulatory safeguard that enables proper assessment of suitability, contraindications, and expectations before any treatment proceeds.
Botox and the masseter: facial slimming and jaw treatment
One of the most widely sought cosmetic applications of botulinum toxin type A in Australia involves the masseter muscle — the large chewing muscle that sits at the angle of the jaw. When this muscle is enlarged (a condition known as masseter hypertrophy), it can create a square or wide lower face. Botulinum toxin treatment to the masseter gradually reduces its bulk, producing a more tapered or oval facial shape over several months.
The same treatment is used for people who clench their jaw or grind their teeth (bruxism), as reducing masseter activity can decrease the force generated during these involuntary behaviours. Clinical evidence supports this application: a 2022 study published in the Journal of Oral Rehabilitation found statistically significant reductions in bruxism-related pain and muscle activity following masseter botulinum toxin treatment.
For those researching this specific application, the facial slimming treatment guide and guide to TMJ and bruxism treatment provide a more detailed overview of the clinical approach, expected timeline, and what to look for in a provider.
Botox for forehead lines and frown lines
Forehead lines and frown lines (the vertical lines that form between the eyebrows) are among the most common cosmetic concerns treated with botulinum toxin. The frontalis muscle produces horizontal forehead lines when it contracts to raise the brows, while the procerus and corrugator supercilii muscles produce frown lines during expressions of concentration, concern, or frustration.
Treatment targeting these areas relaxes the relevant muscles, softening or eliminating visible lines at rest and during expression. The degree of softening depends on baseline line depth — people with deeper, more established lines may retain some residual softening rather than achieving complete resolution, particularly with early treatment sessions.
The forehead wrinkles treatment guide and frown lines treatment guide cover the specific approach to each area, including the distinction between dynamic lines (present only during movement) and static lines (visible at rest), and how treatment strategy differs based on line type and severity.
Botox for brow lifting
A non-surgical brow lift using botulinum toxin works by selectively relaxing the muscles that pull the brow downward — primarily the orbicularis oculi and the depressor supercilii — while preserving or encouraging the activity of the frontalis muscle, which elevates the brow. This creates a subtle upward shift in brow position.
The degree of lift achievable through this method is modest — typically two to four millimetres of elevation — making it best suited to people with mild brow descent rather than significant ptosis. It is not a substitute for surgical brow lifting in people with substantial sagging. For a more detailed overview of what this treatment can and cannot achieve, the non-surgical brow lift guide outlines the clinical approach and realistic outcomes.
Frequently asked questions about botox
Is botox the same as botulinum toxin?
Botox is a brand name for botulinum toxin type A manufactured by Allergan. The terms are often used interchangeably in everyday conversation, but botulinum toxin type A refers to the active molecule, while Botox refers to one specific commercial formulation. Other TGA-registered brands of botulinum toxin type A available in Australia include Dysport and Xeomin.
How quickly does botox work?
Most people begin to notice reduced muscle movement within two to seven days of treatment. Full effect is usually visible at two weeks. For this reason, any review or follow-up assessment is typically scheduled at the two-week mark rather than immediately after treatment.
Can botox be reversed?
Unlike some other cosmetic treatments, botulinum toxin cannot be chemically reversed. It wears off naturally as nerve terminals regenerate over three to six months. This is an important consideration for anyone concerned about results — the outcome is temporary but cannot be expedited if the result is not what the patient expected.
Is botox safe long-term?
Botulinum toxin type A has one of the longest safety records in prescription medicine, with clinical use dating back to the 1980s for conditions such as strabismus and blepharospasm. Long-term cosmetic use has been studied extensively, and the available evidence does not indicate cumulative toxicity at the doses used for aesthetic applications. Some patients who receive regular treatments over several years experience gradual atrophy of targeted muscles, which may result in longer intervals between treatments being required.
Who can administer botox in Australia?
In Australia, botulinum toxin type A is a Schedule 4 prescription medicine. It must be prescribed by a registered medical practitioner. Administration may be performed by a medical practitioner, or in some jurisdictions, by a registered nurse or dental practitioner working within an approved clinical governance framework. The prescribing practitioner must conduct a suitability assessment before treatment proceeds.
Does botox hurt?
The sensation during treatment varies between individuals and treatment areas. Most people describe it as a mild pinching sensation. Topical anaesthetic cream can be applied prior to treatment to reduce discomfort, though many patients find this unnecessary for standard facial applications. Areas such as the masseter may be more sensitive due to the depth of treatment and muscle density.
References
- Therapeutic Goods Administration. (2023). Prescription medicines: Botulinum toxin products. Australian Government Department of Health and Aged Care. https://www.tga.gov.au/
- Carruthers, J., & Carruthers, A. (2021). Botulinum toxin type A for the treatment of glabellar rhytides. Journal of the American Academy of Dermatology, 84(5), 1303–1312.
- Kirkness, C., et al. (2020). Adverse events associated with botulinum toxin in aesthetic medicine: a systematic review. Journal of Cosmetic Dermatology, 19(8), 1940–1948.
- Jokstad, A., et al. (2022). Botulinum toxin for the management of bruxism: a randomised controlled trial. Journal of Oral Rehabilitation, 49(3), 242–251.
Understanding what jowl treatment can realistically achieve is one of the most important steps before committing to any procedure. Results vary depending on the degree of jowling, the treatment approach used, and individual anatomy — and being clear on this from the start leads to far better experiences and outcomes. This post covers what typical before and after results look like, what drives the variation, and how to assess whether what you are seeing in someone else’s results is relevant to your situation.
Quick answer: Non-surgical jowl treatment typically produces a cleaner, more defined jawline with reduced heaviness along the lower face. Results are visible within one to two weeks and last 12 to 24 months or longer depending on the approach. The degree of improvement depends on how much structural change has occurred and which treatment is used — results are significant in suitable candidates, but not equivalent to surgery in advanced cases.
What changes are visible after non-surgical jowl treatment?
The most consistent change people notice after non-surgical jowl treatment is a restoration of jawline continuity. Where there was previously a break or softness along the lower face — particularly the hollow that forms between the chin and the jowl — the area fills in and the jaw reads as a cleaner, more defined line again.
The jowl itself typically appears less prominent, not because it has been removed, but because the surrounding anatomy has been restored to support it better. When the pre-jowl sulcus is no longer hollow and the mandibular line is re-established, the contrast between the jowl and the jaw is reduced — which is what makes jowling look less significant.
Patients also commonly notice an improvement in the overall balance between the lower face and the rest of their face. Because jowling affects the lower third specifically, restoring definition there often makes the whole face appear more harmonious and rested — without changing features in a way that reads as obviously cosmetic.
How much improvement is realistic?
This depends significantly on the starting point. Patients with early to moderate jowling — where the tissue has softened and there is visible pre-jowl hollowing but the tissue has not significantly descended below the jaw — tend to achieve the most noticeable results from non-surgical treatment.
In these cases, well-planned volume treatment can produce a change that patients describe as meaningful and natural-looking. The jawline returns to something closer to how it looked several years earlier, without appearing altered or done.
For patients with more significant jowling — where tissue has dropped well below the jaw border, or where skin laxity is substantial — non-surgical treatment can still improve the appearance, but the degree of correction is more limited. In these situations, surgery offers more definitive results and is worth considering. Our comparison of non-surgical jowl treatment and facelift is worth reading before making a decision in either direction.
The honest framing: non-surgical treatment addresses the visual impact of jowling effectively in suitable candidates. It does not physically reposition descended tissue the way surgery does. Understanding this distinction before treatment ensures expectations are calibrated correctly.
What influences how good the results are?
Several factors determine where your results sit on the spectrum from moderate improvement to highly significant change:
- Degree of jowling at the outset. Earlier intervention produces more pronounced relative results. Someone with mild jowling who acts early will achieve more dramatic visible change than someone with the same treatment applied to advanced jowling.
- Skin quality. Where skin quality is good — meaning there is adequate elasticity and firmness — it responds well to the underlying volume restoration and the results read more cleanly. Where skin quality is significantly compromised, volume treatment alone may not produce the same result.
- Treatment approach. The specific product used, where it is placed, how much is used, and whether collagen stimulating treatment is combined with volume treatment all affect outcome. A comprehensive lower face plan produces better results than a single-area approach in most patients with moderate jowling.
- Lower face anatomy. The proportions of your chin, jawline, and cheeks all affect how jowl treatment reads. In some patients, addressing cheek descent alongside the jowl area — through cheek contouring — produces significantly better results than treating the jowl in isolation. This is part of what we mean when we talk about facial balancing as an approach rather than single-area treatment.
- Practitioner assessment and technique. Where product is placed matters more than how much is used. Strategic placement in the pre-jowl sulcus and along the mandibular line — rather than directly into the jowl — is what produces the most natural and effective results.
[ctaForm]
How quickly do results appear?
Volume-based jowl treatment produces results that are visible relatively quickly. Most patients notice an immediate improvement that settles over a week or so — once any initial swelling from the procedure has resolved.
Collagen stimulating treatment works on a different timeline. Results begin to develop at around six to eight weeks as collagen production is stimulated, and continue improving for three to six months after treatment. This means the result you see immediately after a collagen stimulating session is not the final result — it will continue to improve progressively over the following months.
For patients receiving a combined programme — volume treatment alongside collagen stimulation — the immediate result from the volume component gives a preview of the direction of change, while the collagen stimulating component builds on that over time.
How long do jowl treatment results last?
Volume-based treatment in the jowl and jawline area typically maintains results for 12 to 24 months before a maintenance appointment is recommended. The lower face is a relatively low-movement area compared to, say, the lips — which means product placed here tends to persist longer than in higher-movement zones.
Collagen stimulating treatments generally last 18 to 36 months, and some patients find that successive treatments produce cumulative improvement — meaning each round builds on the collagen foundation laid by the previous one.
Individual factors affect longevity meaningfully. Continued ageing, sun exposure, significant weight changes, and whether you receive maintenance treatment at the right interval all influence how long your results last and how well they hold over time.
The approach we use at our clinics involves concern-based treatment planning — meaning we design each programme around your specific anatomy and what is driving your jowling, rather than applying a standard protocol. This produces more durable outcomes than volume-only or single-session approaches, in our experience.
What do results look like?
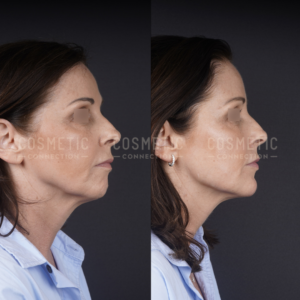
Before and after non-surgical treatment for jowls.

Before and after non-surgical treatment for jowls.
Can results look unnatural?
This is a common and valid concern, and it comes up frequently in consultations. The short answer is: yes, jowl treatment can look unnatural — but this is almost always the result of incorrect product placement rather than an inherent risk of the treatment itself.
The most common error in jowl treatment is placing product directly into the jowl tissue in an attempt to fill or soften it. This typically makes jowling worse, not better — adding volume to an area that already has excess tissue creates more fullness below the jaw, which exaggerates the problem.
Correct technique involves placing product in the areas adjacent to and supporting the jowl — restoring the architecture around it rather than adding to it. The jowl contouring treatment approach we use is anatomy-led: assessment comes before any product selection, and placement decisions are made based on what the individual’s lower face actually needs.
Choosing a doctor-led clinic with specific experience in lower face anatomy significantly reduces the risk of outcomes that look unnatural or overcorrected.
[ctaForm]
Frequently asked questions
How soon after jowl treatment can I see results?
Most patients see clear improvement immediately, with the full effect seen within one week once initial swelling has settled. Collagen stimulating treatment builds over three to six months, so the final result develops progressively rather than immediately.
What do jowl treatment results look like at 12 months?
At 12 months, most patients with well-planned volume treatment still have good definition along the jawline. Some natural softening of the result may begin toward the 12 to 18 month mark, which is when most patients consider a maintenance appointment. Collagen stimulating treatment tends to hold well at this point and may still be improving.
Do jowl treatment results look natural?
When performed correctly, yes. The goal of non-surgical jowl treatment is restoration of the anatomy rather than alteration of features — which produces results that read as the patient looking fresher or younger, not cosmetically altered. Placement technique is the key determinant of natural-looking results.
What happens if I am not happy with my results?
If you are not satisfied with the outcome, the first step is returning to the treating clinician to discuss your concerns. Volume-based treatment using certain product types can be dissolved if needed, providing a pathway to reversal if the outcome is not what was expected. This is one of the reasons product selection and clinician choice matter — not all products in this category are reversible.
Are jowl treatment results permanent?
No. Non-surgical jowl treatment is not permanent. Results from volume-based treatment last 12 to 24 months in most cases, and collagen stimulating treatment 18 to 36 months. Maintenance treatment is required to sustain results over time. The underlying ageing process continues regardless of treatment.
Will I need more treatment than I initially expected?
In most cases, the treatment plan discussed at your initial assessment is accurate. Occasionally, patients with more complex lower face anatomy — or those who have experienced significant volume loss across multiple areas — find that addressing only the jowl area is not sufficient and that the cheek, chin, or jawline also needs attention. A thorough assessment upfront reduces the likelihood of surprises after the first session.
Yes, jowl treatment works — but only when it matches what is actually causing your jowls. Most people have a combination of volume loss in the lower face and changes in skin structure, and the best outcomes come from addressing both. This guide explains what jowls are, why they form, which treatments have the strongest track record, and how to work out what is right for your situation.
If you have noticed your jawline softening, a heaviness appearing below your cheeks, or skin beginning to gather along your lower face — you are not imagining it. Jowling is one of the most common concerns we see across our patient base, and it tends to arrive earlier than most people expect.
Quick answer: Jowl treatment is effective when it targets the right cause. For most people with early to moderate jowling, non-surgical volume treatment can restore definition to the lower face and jawline. For more significant structural descent, surgical options offer more lasting correction. The right approach depends on your anatomy, degree of change, and goals — and should always be assessed in person.
What are jowls and why do they form?
Jowls are the soft tissue changes that occur along the lower face — below the corners of your mouth, extending toward your jaw angle. The skin and tissue soften, the jawline loses its definition, and a fold or heaviness appears that was not there before.
This happens because of changes across multiple layers of the face at once. Bone density in the jaw and chin reduces with age, removing the structural foundation the overlying tissue sits on. Fat compartments in the lower face shift and descend. The ligaments that anchor skin to the underlying structures weaken. Skin itself loses elasticity. The result is that tissue which once sat cleanly along the jawline migrates downward and forward — creating what we recognise as jowling.
It is not simply loose skin. It is a structural change that involves bone, fat, muscle, and ligament together. This is why topical products, facial exercises, and devices that only work on the skin surface tend to produce minimal results — they are addressing the wrong layer.
Several factors accelerate the process: cumulative sun exposure, smoking, significant weight fluctuations, genetics, and — in some cases — certain cosmetic treatments that reduce lower face muscle bulk without prior assessment of the surrounding anatomy.
Does masseter treatment cause jowling?
This is one of the most common questions we hear, and it deserves a direct answer. No, masseter treatment does not cause jowling. However, it can make pre-existing jowls more visible by reducing support.
The masseter muscle sits at the angle of the jaw and provides structural support to the overlying tissue. When this muscle is treated to reduce jaw width or address grinding, it reduces in bulk over several months. In patients who already have lower face volume loss or early laxity, this reduction can remove a layer of support that was helping hold overlying skin in position — making existing jowling more visible.
This does not mean masseter treatment causes jowls or accelerates them. They key is to anticipate who is likely to notice their jowls more after masseter treatment, and discuss this possibility before proceeding.
Should jowls be more visible after masseter treatment, there are two options:
- Let the treatment wear off – the jowls will revert to their pre-treatment appearance
- Perform treatments that support the lower face to reduce jowls. This is more appropriate when one wishes to sustain the masseter results.
What non-surgical treatments are used for jowls?
Non-surgical jowl treatment focuses on restoring the volume and structural support the lower face has lost — rather than attempting to tighten or lift tissue from the outside. This is why volume-based approaches tend to produce more natural and lasting results than energy devices alone in most cases.
The primary approach used in our clinics involves placing treatment product strategically in the areas around and behind the jowl — not directly into the jowl itself. The key areas are the pre-jowl sulcus (the hollow that forms between the chin and the jowl), the mandibular line running toward the jaw angle, and sometimes the chin. By restoring volume to these zones, the jawline regains its continuity and the jowl appears significantly less prominent.
Collagen stimulating treatments are also used in this area, particularly where there is notable reduction in skin quality alongside volume loss. These work differently from standard volume replacement — they stimulate the body’s own collagen production over time, improving skin firmness and reducing laxity from within.
For patients with broader lower face changes — including descending cheeks contributing to jowl formation — cheek contouring may be part of the treatment plan. The midface and lower face work together, and addressing only the jowl area while ignoring midface descent often produces incomplete results.
The table below outlines the main non-surgical approaches and where each sits in the treatment landscape:
| Treatment type | Primary mechanism | Best suited to | Approximate durability |
|---|---|---|---|
| Volume treatment — pre-jowl sulcus and jawline | Restores structural support around the jowl | Early to moderate jowling with adequate tissue quality | 12–24 months |
| Collagen stimulating treatment | Stimulates own collagen production, reduces laxity | Skin quality loss alongside volume change | 18–36 months, builds progressively |
| Combined lower face programme | Volume and collagen stimulation, with cheek support where needed | Moderate jowling, post-weight-loss changes, post-masseter treatment | 18–30 months with maintenance |
You can explore the full range of jowl contouring treatments on our treatment page.
Who is a good candidate for non-surgical jowl treatment?
Non-surgical treatment tends to work best for people in the early to moderate stages of jowling — where there is visible softening of the jawline and some hollowing around the pre-jowl area, but the tissue has not significantly descended beyond the jaw border.
The ideal candidate typically has reasonable skin quality, some remaining structural integrity in the lower face, and realistic expectations about the degree of change achievable without surgery. Age is less relevant than anatomy — we see suitable candidates in their 30s and unsuitable candidates in their 50s, and vice versa.
Candidates who are less likely to achieve satisfying outcomes from non-surgical treatment alone include those with significant skin laxity below the jaw, very heavy jowling where tissue has dropped substantially, or those who have already tried non-surgical approaches and reached the limits of what they can achieve.
Suitability is always assessed in person. A photograph or a description is not enough to make an accurate recommendation in this area of the face.
[ctaForm]
How is jowl treatment different from a facelift?
A surgical facelift addresses jowling by physically repositioning the descended tissue back to where it originated and removing any excess skin. For patients with established, significant jowling — particularly where tissue has dropped well below the jawline — surgery offers a degree of correction that non-surgical treatment cannot match.
Non-surgical volume treatment works differently. Rather than lifting tissue, it restores structural support around the jowl — filling the hollow that makes the jowl appear more prominent and re-establishing the jawline contour. It does not physically reposition descended tissue, but it changes the visual relationship between the jowl and the surrounding anatomy in a way that reads as significant improvement to most observers.
The two approaches are not in competition. Many patients begin with non-surgical treatment and later consider surgery as changes progress. Others find that well-planned non-surgical treatment meets their goals for many years. Our detailed comparison of non-surgical jowl treatment and surgical facelift covers this decision in full.
What results can you expect from jowl treatment?
The most consistent result from well-planned non-surgical jowl treatment is a cleaner, more defined jawline — with the heaviness or softness along the lower face visibly reduced. Most patients also notice an improvement in the overall balance of the lower face, as the area between the chin and jaw angle regains its continuity.
Results from volume treatment are typically visible within one to two weeks of the procedure, once any initial swelling has resolved. Collagen stimulating treatments build more gradually over three to six months as the body’s own tissue response develops — meaning results continue to improve after the treatment itself is complete.
Longevity depends on the treatment approach used, the degree of change at the outset, and individual factors including how quickly someone continues to age after treatment. Most patients return for maintenance treatment at 12 to 24 months.
For a closer look at what outcomes look like in practice, see our post on jowl treatment before and after results.
The broader context of facial balancing is also worth understanding — because jowling rarely exists in isolation. Changes in the cheeks, marionette area, and chin all contribute to how jowling reads on the face, and treating only one element often produces results that feel incomplete.
How much does jowl treatment cost in Australia?
The cost of jowl treatment varies considerably depending on the approach used, the complexity of the lower face anatomy, and the number of areas being addressed. A single-area approach to a mild pre-jowl sulcus will sit at a different price point from a comprehensive lower face programme addressing the jawline, chin, and cheeks together.
At our clinics, we use flat-fee pricing — meaning the cost is agreed before treatment, with no variable charges based on product volume. This makes it straightforward to plan your treatment without unexpected costs.
For a full breakdown of jowl treatment costs and what is included, see our dedicated jowl treatment cost guide. You can also view our full flat-fee services list for an overview of how our pricing works.
[ctaForm]
Frequently asked questions
At what age do jowls typically start to appear?
Jowling can begin showing in the mid-30s, and in some people as early as their late 20s — particularly those with genetics that predispose them to lower face volume loss, or with significant sun exposure history. Australia’s UV environment accelerates structural facial changes compared to many other countries, meaning earlier onset is more common here than in the UK or USA.
Can you fix jowls without surgery?
For early to moderate jowling, yes. Non-surgical volume treatment and collagen stimulating approaches can significantly reduce the appearance of jowls by restoring structural support around the pre-jowl area and jawline. Surgery offers a greater degree of correction for established or significant jowling, but is not the only effective option.
Does masseter treatment always cause jowls?
No. Masseter treatment is associated with jowling in a subset of patients — specifically those who already have jowls. In patients without jowls, masseter treatment will not cause them. In those with jowling and skin laxity, it may make them more obvious, but will not accelerate their development. Should jowls be more noticeable after masseter treatment, you can either treat the jowling, or let the masseter treatment wear off. Proper suitability assessment beforehand is the key factor.
How long does jowl treatment last?
Volume-based treatment typically lasts 12 to 24 months before maintenance is needed. Collagen stimulating treatment tends to last longer — 18 to 36 months — and may improve further over the first six months after treatment as the collagen response matures. Individual factors including ongoing ageing, lifestyle, and treatment approach all affect longevity.
Is jowl treatment painful?
Discomfort is generally minimal. Treatment in this area of the face is well tolerated by most patients. Numbing cream is applied beforehand and the procedure itself typically takes 20 to 40 minutes depending on the areas treated. Some mild swelling or tenderness afterward is normal and resolves within a few days.
What is the difference between jowls and a double chin?
Jowls refer to the soft tissue changes along the lower face and jawline — the heaviness or descent that appears below the corners of your mouth and along the jaw. A double chin refers to fullness beneath the chin itself, typically caused by submental fat. The two concerns can co-exist but involve different anatomy and are addressed by different treatments.
Nasolabial folds and marionette lines are two of the most common lower face concerns we assess at Cosmetic Connection — and they are frequently confused with each other. They sit in the same region of the face, share some underlying causes, and often appear together. But they are anatomically distinct, they create different visual effects, and they are not always treated the same way. This guide explains the differences clearly and covers what treatment for each actually involves.
Quick answer: Nasolabial folds run from the sides of the nose to the corners of the mouth. Marionette lines run downward from the corners of the mouth toward the chin. Both deepen with age due to volume loss and structural changes in the lower face — but marionette lines tend to appear later and are more strongly associated with jowl formation and a downturned resting expression. Both can be addressed with non-surgical cosmetic treatment, and both are frequently treated in the same appointment as part of a lower face plan.
Where each line sits on the face
The simplest way to distinguish these two concerns is by location.
Nasolabial folds — also called smile lines or laugh lines — are the creases that extend from the outer base of the nose diagonally downward to the corners of the mouth. They are present to some degree in every face and become a concern when they are visible and prominent at rest, creating a tired or aged appearance in the midface.
Marionette lines — clinically called melomental folds — are the vertical creases that extend downward from the corners of the mouth toward the chin. The name comes from the pronounced lower facial lines of a marionette puppet. When deep, they create the impression of a downturned or unhappy expression at rest, even when the face is completely relaxed.
The two sets of lines meet at the corners of the mouth. Nasolabial folds end where marionette lines begin — which is part of why they are so often seen together and why a lower face assessment considers both simultaneously.
What causes each one — and how the causes differ
Both lines deepen through similar broad mechanisms — volume loss, reduced structural support, and skin changes over time — but the specific anatomical drivers are somewhat different for each.
Nasolabial folds
Nasolabial folds deepen primarily because of changes in the midface. As the fat pads of the cheek thin and descend with age, and as bone in the upper jaw recedes, the overlying tissue loses its structural support and the fold appears deeper. Research published in Aesthetic Surgery Journal (Minelli et al., 2023) identifies fat deflation and muscle atrophy in the perioral region — causing up to a 40% reduction in soft tissue thickness — alongside upper jaw bone resorption as the two primary mechanisms. Nasolabial folds tend to become noticeable earlier, often from the late twenties or early thirties onward in people with predisposing facial structure.
Marionette lines
Marionette lines involve a more complex anatomical picture. Research published in Skin Research and Technology (Hong et al., 2024) identifies their formation as a result of bone resorption of the lower jaw, gravitational forces on descending fat compartments, ligament tethering at the corners of the mouth, muscle compression from the depressor anguli oris, and progressive skin ageing — all acting simultaneously. Facial volume loss during ageing significantly impacts the definition of the jawline, contributing to skin sagging, jowl formation, and the development of prominent marionette lines. They tend to appear later than nasolabial folds — typically becoming noticeable from the mid-forties onward — and are more strongly associated with lower face heaviness and jowling.
In our clinical experience, patients who present with significant marionette lines almost always have some degree of nasolabial fold deepening as well — because the upstream causes, particularly midface volume loss and lower face descent, drive both simultaneously.
How the visual effect differs
Understanding the different visual effect of each concern helps explain why people find them bothersome in different ways.
Deep nasolabial folds at rest tend to create an aged or tired appearance in the midface. They frame the mouth in a way that can make the face look heavy or drawn. Because they become more pronounced during expression, patients sometimes notice them particularly in photos taken while smiling.
Deep marionette lines create a different impression — one that is often described as sad, stern, or unhappy at rest. The downward direction of the line pulls the visual weight of the lower face toward the chin and jaw, and when prominent, they contribute to jowling and a loss of the clean lower face contour that is associated with a more youthful appearance.
Both affect how others perceive your mood and energy level from your resting face — which is why they are consistently among the concerns that patients find most affecting day to day.
[ctaForm]
How treatment for each differs
Because the anatomical drivers and locations of nasolabial folds and marionette lines are different, the treatment approach for each has some important distinctions — even though both involve non-surgical volume support.
Treating nasolabial folds
As covered in our complete guide to smile lines treatment, the most effective approach for nasolabial folds often involves addressing the midcheek and upstream volume loss rather than simply filling the crease directly. Restoring volume to the cheek lifts the overlying tissue that has descended and reduces the apparent depth of the fold from above, producing a more natural-looking result than treating the fold in isolation. In many cases, a combination of midcheek volume and direct fold treatment produces the best outcome.
Treating marionette lines
Marionette lines respond differently. Because their formation involves ligament tethering at the corners of the mouth, jowl fat accumulation, and lower jaw bone resorption, treatment typically needs to address the lower face as a structural unit — not just the line itself. Volume placed in the pre-jowl area and along the jawline can help lift the tissue that has descended and reduce both the marionette line and the associated jowling. In some cases, chin support is also part of the treatment plan. Our marionette lines treatment page covers this approach in more detail.
When both are treated together
Treating nasolabial folds and marionette lines in the same appointment is common and clinically appropriate. The lower face functions as a system — changes in one area affect the appearance of adjacent areas. A plan that addresses both simultaneously, as part of a broader lower face assessment, typically produces a more balanced and natural-looking result than treating each in isolation at separate times. This is the approach we take through facial balancing at Cosmetic Connection.
Side by side: nasolabial folds vs marionette lines
| Nasolabial folds | Marionette lines | |
|---|---|---|
| Location | Nose to corners of mouth | Corners of mouth to chin |
| Clinical name | Nasolabial folds | Melomental folds |
| When they typically appear | Late 20s–30s onward | Mid-40s onward typically |
| Primary cause | Midface volume loss; cheek fat pad descent; upper jaw bone resorption | Lower jaw bone resorption; ligament tethering; jowl fat descent; lower face volume loss |
| Visual effect | Tired or aged midface; more pronounced during expression | Downturned or unhappy resting expression; contributes to jowling |
| Associated concerns | Cheek volume loss; under-eye hollowing | Jowls; lower face heaviness; jawline loss |
| Treatment focus | Midcheek and fold volume support | Pre-jowl, jawline, and lower face structural support |
| Can they be treated together? | Yes — often recommended in the same appointment | |
What to expect if you are assessed for both
If you present to assessment at our clinics with both nasolabial folds and marionette lines as concerns, the consultation will evaluate the whole lower face — not just each line in isolation. This includes the state of your midcheek volume, the degree of lower face descent, the depth and character of each set of lines, your skin quality and laxity, and how the two concerns interact visually.
From that assessment, we will recommend a plan that addresses the actual drivers of your concern — which may involve treating both in the same appointment, prioritising one over the other based on what is most affecting your appearance, or recommending a staged approach if the level of correction needed is more significant.
Costs for treating both concerns in a single appointment will vary depending on the areas addressed and the approach used. Our flat-fee pricing structure means the total cost is confirmed at consultation with no variable charges applied during the procedure. For a breakdown of typical costs for smile lines treatment specifically, see our smile lines treatment cost guide.
Can both concerns be treated non-surgically?
In most cases, yes — with the understanding that results are a softening of the lines rather than their complete elimination. The best candidates for non-surgical treatment of both nasolabial folds and marionette lines are those whose concerns are primarily driven by volume loss and structural descent rather than significant skin laxity.
Where skin laxity is the dominant factor — particularly with advanced marionette lines and jowling — non-surgical volume support alone may produce a limited result. In these cases, a surgical consultation may be the more appropriate recommendation, or a carefully considered combination approach. The assessment will clarify which category applies to your anatomy.
For a detailed breakdown of who is and is not a good candidate for non-surgical treatment of nasolabial folds, see our nasolabial fold treatment suitability guide.
[ctaForm]
Frequently asked questions
Are nasolabial folds and marionette lines the same thing?
No. They are two distinct sets of lines in adjacent areas of the lower face. Nasolabial folds run from the nose to the corners of the mouth. Marionette lines run from the corners of the mouth downward toward the chin. They share some underlying causes and frequently appear together, but they involve different anatomical structures and are not always treated the same way.
Which appears first — nasolabial folds or marionette lines?
Nasolabial folds typically become noticeable earlier, often from the late twenties or early thirties onward in people with predisposing facial structure. Marionette lines tend to appear later — most commonly from the mid-forties onward — because their formation is more dependent on lower face descent and jaw bone changes that develop over a longer period.
Do I need to treat both at the same time?
Not necessarily. If one concern is significantly more prominent than the other, it may make clinical sense to prioritise that area first and reassess. However, because both sets of lines are driven by related structural changes in the lower face, treating them together in the same appointment often produces a more balanced result — and may be more cost-effective than two separate appointments.
Will treating my nasolabial folds also improve my marionette lines?
Partially, in some cases. Restoring midcheek volume can lift the lower face tissue and reduce the appearance of marionette lines to some degree — because it addresses upstream descent that contributes to both concerns. But a treatment plan specifically targeting marionette lines directly, including the pre-jowl area and lower face, will produce a more complete result for that specific concern.
Are marionette lines harder to treat than nasolabial folds?
They are generally more complex to treat well. The ligament tethering at the corners of the mouth and the associated jowl formation mean that treatment needs to address the lower face as a structural unit rather than simply filling the line. In our clinical experience, the most common reason marionette line treatment elsewhere produces a limited or unnatural result is that the lower face was not treated as a whole — volume was placed in the line without addressing the structural context around it.
References
- Minelli L, Brown CP, Warren RJ, van der Lei B, Mendelson BC, Little JW. (2023). Lifting the Anterior Midcheek and Nasolabial Fold: Introduction to the Melo Fat Pad Anatomy and Its Role in Longevity and Recurrence. Aesthetic Surgery Journal, 43(9), 941–954. https://doi.org/10.1093/asj/sjad126
- Hong J, et al. (2024). Why do marionette lines appear? Exploring the anatomical perspectives and role of thread-based interventions. Skin Research and Technology. https://doi.org/10.1111/srt.13676
- Yi KH, Park SY. (2024). Marionette lines correction with volumizing threads. Journal of Cosmetic Dermatology. https://pmc.ncbi.nlm.nih.gov/articles/PMC11626340/
Marionette lines are the vertical creases that run from the corners of the mouth down toward the chin. They are a natural result of facial ageing, and they respond well to the right non-surgical cosmetic treatment — provided the approach addresses what is actually causing them, not just the lines themselves. This post explains what drives marionette line formation, how treatment works, what results are realistic, and what to look for when choosing a provider in Australia.
Quick answer: Marionette lines form as the face loses volume and structural support with age, causing the skin around the lower face to descend and fold. Non-surgical cosmetic treatments can soften and lift these lines by restoring volume in the right areas. Results are visible from the first treatment and typically last 12 to 18 months depending on the approach used and individual factors.
What are marionette lines and why do they form?
Marionette lines are the folds that extend downward from the corners of the mouth toward the jawline. The name comes from marionette puppets, which have hinged lower jaws — the lines create a similar visual effect, often giving the face a downturned or drawn expression even when relaxed.
They are not caused by any single factor. According to research published in Skin Research and Technology (2024), marionette line formation involves a complex interplay of anatomical, physiological, and age-related changes. In practical terms, this means several things are happening at once: fat compartments in the midface shift downward under gravity, bone density in the jaw reduces, the skin loses elasticity as collagen production slows, and specific muscles — including the depressor anguli oris — exert a downward pull at the corners of the mouth.
The result is a fold that deepens progressively with age. In the early stages it may appear only during facial movement. Over time it becomes a static feature — present at rest, and more prominent in certain lighting.
It is worth understanding that marionette lines and smile lines treatment address two separate structures. Smile lines (nasolabial folds) run from the nose to the corners of the mouth. Marionette lines begin at the mouth corners and continue downward. They often develop together, and they share some underlying causes — but they are anatomically distinct and treating one does not automatically address the other. Read more about nasolabial folds vs marionette lines.
How are marionette lines different from nasolabial folds?
Marionette lines sit below the mouth; nasolabial folds sit above it. Both are signs of midface descent, but they are driven by different anatomical structures and require different treatment approaches.
| Feature | Marionette lines | Nasolabial folds (smile lines) |
|---|---|---|
| Location | Mouth corners to chin/jawline | Nose to mouth corners |
| Primary cause | Lower face volume loss, muscle pull, skin laxity | Midface fat pad descent, cheek volume loss |
| Effect on appearance | Downturned, drawn, or sad expression at rest | Aged, tired appearance; deepens with smiling |
| Treatment area | Lower face, pre-jowl region, corners of mouth | Midface, cheeks, nasolabial groove |
| Often treated together? | Yes — lower and mid-face ageing frequently overlap | Yes — same ageing cascade |
For a detailed explanation of nasolabial fold treatment, including how smile lines are assessed and approached differently, that is covered separately.
In our clinical experience, patients often present believing they only have one concern when assessment reveals both are present and contributing to the overall appearance. A thorough consultation will identify which structures need addressing and in what order.
What causes marionette lines to get worse over time?
Marionette lines deepen for the same reasons that all signs of facial ageing progress — but in the lower face, a specific combination of factors accelerates that process.
Volume loss in the midface is a significant driver. As the cheek fat compartments descend with age, support is removed from the structures below. This is why midface volume loss so often appears alongside marionette lines — the two concerns are anatomically connected, even when patients only notice one. Research published in Contemporary Clinical Dentistry (Tanaka et al., 2023) confirmed that deepened perioral folds — including marionette lines — are among the primary visual cues observers use to assess age and attractiveness, with the mouth area drawing disproportionate attention in faces showing these changes.
Other contributing factors include:
- Reduced bone density in the jaw and chin, which reduces structural scaffolding for overlying tissue
- Loss of skin elasticity as collagen and elastin production slows — typically beginning in the mid-20s and accelerating after 40
- Repeated downward muscle activity from the depressor anguli oris muscle, which actively pulls the corners of the mouth downward
- Genetics — some people develop prominent marionette lines earlier due to facial anatomy and inherited patterns of fat distribution
- Sun exposure, smoking, and significant weight fluctuation, which accelerate collagen breakdown and skin laxity
Understanding what is driving the lines in a specific person matters because it informs which treatment approach will work best. Treating marionette lines well is not simply a matter of filling the groove.
Cosmetic treatment options for marionette lines
Non-surgical cosmetic treatments are the most practical and widely chosen approach for marionette lines in Australia. They deliver visible results without surgical recovery, and they are reversible — an important consideration for a treatment area where precise placement is essential.
The two main categories of non-surgical treatment are volume restoration using cosmetic treatments, and collagen stimulation. In practice, many people benefit from a combination of both, used across a planned treatment schedule rather than a single session.
Volume restoration treatments
Volume restoration is the most immediate approach. Treatment is placed strategically around the lower face — not only in the marionette groove itself, but in the surrounding structures that are contributing to the descent. This might include the pre-jowl area, the corners of the mouth, and sometimes the midface, depending on what the assessment reveals.
A prospective multicentre clinical trial published in the Journal of Cosmetic Dermatology (Fundaro et al., 2023) reported a treatment success rate of 94.4% for marionette lines at three weeks post-treatment, with 88% of patients maintaining successful outcomes at 18 months. These figures reflect a structured, assessed approach — not a single-point fill of the line itself.
Results from volume restoration treatments for marionette lines are visible immediately. Longevity depends on the product used, the volume placed, individual metabolism, and lifestyle factors, but most people see results that last 12 to 18 months.
Collagen stimulating treatments
For people with more advanced marionette lines, or those who prefer a gradual improvement over time, collagen stimulating treatments are an alternative or complementary approach. Rather than adding volume directly, these treatments trigger the body’s own collagen production, building structural support gradually over several months.
The trade-off is that results are not immediate — improvement develops over three to six months — but the quality of skin and structural support achieved can be more durable. We see this approach working well for patients in their late 40s and beyond, where skin quality and structural loss are both present rather than volume loss alone.
What about cosmetic muscle-relaxing treatments for marionette lines?
This is one of the most common questions we receive. Muscle-relaxing cosmetic treatments work by reducing the activity of muscles that cause lines and creases. For marionette lines, the depressor anguli oris muscle actively pulls the corners of the mouth downward, and treating this muscle can form a useful part of a comprehensive plan. However, muscle-relaxing treatment alone is unlikely to produce significant improvement for established marionette lines — these are primarily volume and structural concerns, not purely movement-driven lines. The two approaches are often combined.
| Treatment approach | How it works | Onset of results | Typical longevity | Best suited to |
|---|---|---|---|---|
| Volume restoration | Restores lost volume, lifts and supports surrounding tissue | Immediate | 12–18 months | Moderate to deep marionette lines; most age groups |
| Collagen stimulation | Triggers natural collagen production over time | 3–6 months | Up to 24 months | Advanced lines; skin quality concerns; late 40s+ |
| Muscle-relaxing treatment | Reduces downward pull of depressor anguli oris | 5–14 days | 3–4 months | Downturned mouth corners; as an adjunct to volume treatment |
| Combined approach | Two or more of the above, sequenced appropriately | Immediate + progressive | 12–24 months | Most moderate-to-advanced presentations |
[ctaForm]
What results are realistic — and what does the process look like?
Realistic expectations are one of the most important things to establish before any treatment. Marionette lines can be softened significantly — most patients describe looking noticeably fresher and less drawn without appearing to have had anything done. Full elimination of deep, established lines is not the appropriate goal, and any provider suggesting otherwise warrants caution.
The treatment process at our clinics is planned around the concern, not the product. Before any treatment is recommended, an assessment determines the contributing factors — which structures have lost volume, how much skin laxity is present, and whether muscle activity is a significant driver. From there, a treatment plan is built that addresses the root causes, not just the visible line.
On the day of treatment, the procedure itself is straightforward. Topical numbing is applied beforehand. The treatment takes approximately 30 to 45 minutes. Most people have some mild swelling and occasional bruising in the days following, which typically resolves within a week. The treated area should be left alone for several hours after treatment, and strenuous exercise and alcohol avoided for 24 to 48 hours.
We have seen patients who were treated with volume placed directly into the marionette groove — without addressing the surrounding structural deficits — end up with results that looked unnatural or short-lived. Our approach accounts for the full lower face picture, which consistently produces results that look right at every angle and hold for longer.
How much does marionette line treatment cost in Australia?
The cost of marionette line treatment in Australia varies depending on the treatment approach, the volume required, and the clinic you choose. At Cosmetic Connection, marionette line treatment is available on a flat-fee basis, with treatment costs ranging from $1,500 to $2,500 depending on the treatment approach and volume required.
That range reflects the reality that no two presentations are the same. A person with early, mild marionette lines will require less treatment than someone with deeper, more established lines across both the lower face and pre-jowl region. The consultation process establishes what is appropriate for your specific situation before any commitment is made.
A few things worth understanding when comparing costs:
- Per-unit or per-syringe pricing models can make it difficult to predict the total cost upfront — flat-fee pricing removes that uncertainty
- The cheapest option is rarely the best value in this treatment area — the lower face is complex anatomy where precision matters
- A consultation that includes a genuine suitability assessment is a signal of a considered, patient-first approach
For a full overview of our pricing structure, visit our flat-fee services page.
What to look for in a marionette line treatment provider in Australia
Provider selection is one of the most consequential decisions in this process. The lower face is a complex treatment area with significant anatomical variation between individuals and important vascular structures that require anatomical knowledge and careful technique.
In our experience, the questions worth asking before committing to treatment are:
- Is a suitability assessment part of the process? A provider who moves directly to recommending volume without first assessing your anatomy and the underlying causes of your lines is not approaching this thoughtfully.
- Is the treatment plan concern-based or product-based? The goal should be to address what is causing your marionette lines — not to sell a particular volume of a particular product.
- Who is performing the treatment? In Australia, cosmetic treatments should be performed by or under the direct supervision of a qualified medical practitioner. Doctor-led clinics carry a higher standard of clinical oversight and the ability to manage complications if they arise.
- Is there a guarantee or aftercare process? A clinic confident in its outcomes will stand behind its results.
A systematic review published in Aesthetic Plastic Surgery (Kyriazidis et al., 2024), analysing 48 high-evidence studies on cosmetic treatment adverse events, identified that complication rates are significantly associated with provider experience and anatomical knowledge. Choosing a qualified, experienced provider is the single most important risk-reduction decision you can make.
At our clinics across Sydney and Melbourne, every marionette line assessment is conducted by a doctor, and every treatment plan is built around your specific presentation — not a standard protocol.
[ctaForm]
Frequently asked questions
Are marionette lines the same as smile lines?
No. Smile lines (also called nasolabial folds) run from the nose to the corners of the mouth. Marionette lines begin at the mouth corners and extend downward toward the chin. They share some underlying causes and often appear together, but they are distinct structures that require separate treatment assessment.
Do cosmetic treatments hurt?
Most people tolerate marionette line treatment well. Topical numbing cream is applied before treatment, and many products contain a local anaesthetic. Some mild discomfort, pressure, or a stinging sensation during treatment is normal. Pain is not a common feature of a well-managed procedure.
How long does marionette line treatment last?
Results from volume restoration treatments typically last 12 to 18 months. Collagen stimulating approaches can provide support for up to 24 months. Longevity varies with individual metabolism, lifestyle factors, and the volume and approach used. Most people return for a maintenance treatment annually or as their results start to soften.
Can marionette lines be prevented?
The underlying processes — bone resorption, fat compartment descent, and collagen loss — cannot be fully prevented. However, consistent sun protection, avoiding smoking, maintaining a stable weight, and addressing early volume changes before they progress are all approaches that can slow the development and deepening of marionette lines over time.
Is treatment reversible if I am not happy with the result?
Volume restoration treatments used at Cosmetic Connection can be dissolved if needed, which means the treatment is not permanent. This is one reason volume restoration is the preferred first approach in a treatment area as anatomically nuanced as the lower face — the ability to adjust or reverse the result matters.
Who is suitable for marionette line treatment?
Most adults who are bothered by the appearance of marionette lines and are in good general health are suitable for treatment. Suitability assessment at consultation considers the severity of the lines, the contributing anatomical factors, skin quality, and medical history. Some presentations are better addressed with a staged plan rather than a single session, and some are not well suited to non-surgical treatment — which a proper consultation will identify.
References
- Tanaka OM, Cavassin LD, Gasparello GG, et al. (2023). The esthetics of the nasolabial fold and age in the elderly via eye-tracking. Contemporary Clinical Dentistry, 14(1):18–24. https://pmc.ncbi.nlm.nih.gov/articles/PMC10209770/
- Stefura T, Kacprzyk A, Droś J, et al. (2021). Tissue fillers for the nasolabial fold area: a systematic review and meta-analysis of randomised clinical trials. Aesthetic Plastic Surgery. PMID: 34255156.
- Ehlinger-David A, et al. (2023). A prospective multicenter clinical trial evaluating the efficacy and safety of a hyaluronic acid-based filler with Tri-Hyal technology in the treatment of lips and the perioral area. Journal of Cosmetic Dermatology, 22(2):464–472. https://pmc.ncbi.nlm.nih.gov/articles/PMC10087550/
- Kyriazidis I, Spyropoulou GA, Zambacos G, et al. (2024). Adverse events associated with hyaluronic acid filler injection for non-surgical facial aesthetics: a systematic review of high level of evidence studies. Aesthetic Plastic Surgery, 48:719–741. https://doi.org/10.1007/s00266-023-03465-1
- Skin Research and Technology (2024). Why do marionette lines appear? Exploring the anatomical perspectives and role of thread-based interventions. https://pmc.ncbi.nlm.nih.gov/articles/PMC10993050/
Not everyone with nasolabial folds is a good candidate for non-surgical treatment — and not everyone who is suitable will get the same type of plan. Suitability depends on what is causing your folds to deepen, the depth and character of the fold itself, your skin quality, and what you are hoping to achieve. This guide walks through the key factors that determine candidacy so you can approach your consultation with realistic expectations.
Quick answer: Good candidates for nasolabial fold treatment are typically people whose folds are visible at rest, whose concern is driven primarily by midface volume loss or fat pad descent, who have realistic expectations about softening rather than eliminating the fold, and who are in generally good health. People whose folds are driven mainly by significant skin laxity, or who expect complete elimination of the crease, are less likely to be well-suited to non-surgical treatment alone.
What makes someone a good candidate?
The most straightforward way to assess candidacy is to understand what non-surgical nasolabial fold treatment does well — and where its limitations lie. Candidates who fit the following profile tend to get the most satisfying results.
The fold is visible at rest
Dynamic lines — those that only appear during expression — tend to respond differently to volume support than folds that are present even when the face is completely relaxed. If your nasolabial fold is clearly visible at rest and bothers you in photos or in the mirror without any expression, that is a strong indicator that structural volume support may meaningfully improve its appearance.
Volume loss is the primary driver
Research published in Aesthetic Surgery Journal (Minelli et al., 2023) confirms that nasolabial folds deepen primarily through two mechanisms — fat pad deflation and bone resorption in the upper jaw. Both of these are structural changes that volume support can directly address. If your fold deepening is driven primarily by these mechanisms, you are likely to be a good candidate. If it is driven mainly by skin laxity, the picture is more nuanced.
Expectations are realistic
Non-surgical treatment softens nasolabial folds — it does not eliminate them. The fold is a normal anatomical feature. The goal of treatment is a more rested, refreshed appearance in the midface, with the fold reduced to a depth that no longer concerns you at rest. Patients who understand and accept this distinction — and are not expecting their face to look the way it did at 20 — tend to be the most satisfied with their outcomes.
General health is stable
Certain medical conditions, autoimmune conditions, active infections, and medications can affect candidacy or timing. These are assessed at consultation. Pregnancy and breastfeeding are contraindications to treatment. A history of cold sores or herpes simplex in the perioral area is worth disclosing, as treatment in or near this region may trigger an outbreak without appropriate prophylaxis.
Who may not be a good candidate?
Equally important is understanding where non-surgical nasolabial fold treatment is unlikely to achieve the desired result — so patients are not recommended a treatment that is not going to help them.
Significant skin laxity
When the skin itself has substantially thinned, loosened, and lost its structural attachment to the underlying tissue, adding volume alone can sometimes make the area look heavier rather than more lifted. In these cases, the skin laxity needs to be addressed — either with a skin-quality approach, a surgical consultation, or a very carefully planned combination strategy. A non-surgical treatment that places volume in the presence of significant laxity can, in some cases, worsen the appearance rather than improve it.
Very deep structural folds present since youth
Some people have deep nasolabial folds from an early age — not because of volume loss, but because of their underlying facial structure. These folds are present during expression from childhood and simply become more visible with age because the surrounding tissue provides less support. Non-surgical volume treatment can soften these folds to some degree, but the result may be less dramatic than in patients whose fold depth is primarily age-related. Expectations need to be calibrated accordingly at consultation.
Body dysmorphia or disproportionate distress
When the level of distress about a concern is significantly out of proportion to the clinical appearance of the fold, non-surgical treatment is unlikely to provide lasting satisfaction regardless of the outcome. Our suitability-first approach means we discuss this honestly at consultation, and may recommend other forms of support before or instead of treatment. This is not a reason to feel dismissed — it is a reflection of clinical responsibility.
[ctaForm]
How age affects candidacy
Nasolabial fold treatment is not age-restricted, but the drivers of fold deepening — and therefore the most appropriate approach — change across different life stages.
| Age group | Typical drivers of fold depth | Candidacy notes |
|---|---|---|
| 20s–early 30s | Facial structure; limited volume loss | Assessment is important — structural folds may be less responsive. Suitability assessed individually. |
| Mid 30s–40s | Early midface volume loss; beginning of fat pad descent | Often good candidates, particularly for midcheek volume support. Results tend to be natural and well-maintained. |
| 50s–60s | Moderate to significant volume loss; some skin laxity | Good candidates where laxity is not the dominant factor. Combination approaches often most appropriate. |
| 70s+ | Significant structural change; skin laxity more prevalent | Suitability assessed individually. Volume alone may be insufficient where laxity is advanced. Surgical consultation may be appropriate. |
Questions to ask yourself before your consultation
Going into a consultation having already reflected on these questions will help you get more out of the assessment conversation.
- Is the fold that bothers me visible at rest, or mainly when I smile or make expressions?
- When I look in the mirror or at photos, is the fold the main thing I notice — or is it part of a broader concern about the midface, cheeks, or lower face?
- What does “improvement” look like to me? Am I expecting the fold to disappear entirely, or am I hoping for it to be less noticeable?
- Has this concern been present since I was young, or has it developed or deepened noticeably in the last few years?
- Am I currently pregnant, breastfeeding, or taking any medications that affect the immune system or blood clotting?
Being honest about your answers to these questions — both with yourself and with your treating practitioner — is the foundation of a good outcome. Suitability assessment is not a formality. It is the most important step in the process.
What the suitability assessment at Cosmetic Connection involves
At our clinics, the assessment for nasolabial fold treatment involves a structured face-to-face evaluation of your fold depth and character, the state of your midface and cheek volume, skin quality and laxity, and the balance of your face as a whole. We discuss your goals, your history with any previous cosmetic treatments, and any relevant medical background.
If treatment is appropriate, we confirm the plan and the cost — using our flat-fee pricing structure — before anything proceeds. If treatment is not the right fit at this point, we explain why and, where relevant, discuss what alternatives or timing adjustments might better serve your situation. Our full approach to this process is explained on our patient journey page.
For a broader overview of the treatment itself, our complete guide to smile lines treatment covers what the treatment involves, how long results last, and how it compares to other approaches.
[ctaForm]
Frequently asked questions
Can I have nasolabial fold treatment if I have had it before elsewhere?
Yes, in most cases. If you have had previous treatment in the area, we will assess the current state of your anatomy before recommending anything. In some cases, previous treatment that has not fully resolved may need to be considered in the planning. Disclosing your treatment history at consultation is important so the assessment is accurate.
Am I too young for smile lines treatment?
There is no minimum age restriction, but treatment in younger patients needs to be assessed carefully. If a fold is present primarily because of facial structure rather than age-related volume loss, the result from non-surgical treatment may be more limited. A thorough assessment will clarify whether treatment is likely to achieve the result you are hoping for.
Am I too old for smile lines treatment?
Age alone does not determine suitability. The key factor is the nature and driver of the fold — not the patient’s age. In patients where significant skin laxity is the dominant factor, a different approach may be needed. But many patients in their 60s and beyond are excellent candidates for non-surgical treatment when the anatomy is appropriate.
What if I am not suitable for non-surgical treatment?
If the assessment finds that non-surgical treatment is unlikely to achieve your goals — because of skin laxity, anatomy, or the nature of your concern — we will discuss alternatives. This might include a referral for surgical assessment, a different non-surgical approach, or a recommendation to defer treatment. Being told you are not a good candidate is not a rejection — it is honest clinical guidance that protects you from investing in a treatment that will not deliver what you are hoping for.
How do I know if my folds are caused by volume loss or skin laxity?
A face-to-face assessment is the only reliable way to determine this. A rough self-test: gently lift the skin of your cheek upward with your fingers. If the fold softens significantly when you do this, volume loss and midface descent are likely contributors. If the fold remains deep regardless, skin laxity may be a more dominant factor. This is a guide only — it does not replace clinical assessment.
References
- Minelli L, Brown CP, Warren RJ, van der Lei B, Mendelson BC, Little JW. (2023). Lifting the Anterior Midcheek and Nasolabial Fold: Introduction to the Melo Fat Pad Anatomy and Its Role in Longevity and Recurrence. Aesthetic Surgery Journal, 43(9), 941–954. https://doi.org/10.1093/asj/sjad126
- Stefura T, Kacprzyk A, Droś J, Krzysztofik M, Skomarovska O, Fijałkowska M, Koziej M. (2021). Tissue Fillers for the Nasolabial Fold Area: A Systematic Review and Meta-Analysis of Randomized Clinical Trials. Aesthetic Plastic Surgery, 45(5), 2300–2316. https://doi.org/10.1007/s00266-021-02439-5
- Aesthetic Surgery Journal Open Forum. (2025). Quantitative Assessment of Nasolabial Fold Characteristics Across Age Groups. Oxford Academic. https://academic.oup.com/asjopenforum/article/doi/10.1093/asjof/ojaf075/8180122
Smile lines treatment in Australia typically costs between $1,500 and $2,500 per appointment. The variation depends on the treatment approach, whether the midcheek is treated alongside the fold itself, and the extent of volume correction required. This guide explains what drives the cost, what is included, and what to look for when comparing providers.
Quick answer: Non-surgical smile lines treatment in Australia ranges from approximately $1,500 to $2,500 per appointment at reputable doctor-led clinics. Treating the fold in isolation typically sits at the lower end of this range. A plan that also addresses midface and cheek volume — which tends to produce a more natural result — sits at the higher end. At Cosmetic Connection, pricing is flat-fee, meaning the cost is confirmed before treatment begins with no variable charges applied during the procedure.
What affects the cost of smile lines treatment?
Smile lines treatment cost is not uniform — several factors influence where an individual appointment falls within the typical pricing range.
- Treatment area: Treating the fold directly is a more contained procedure than addressing the fold and the midcheek together. A plan that incorporates broader midface volume restoration will cost more than one focused solely on the crease.
- Fold depth and volume required: Deeper, more established folds or more significant volume loss require more correction to achieve the same degree of softening as a shallower fold. The extent of correction needed influences the overall cost.
- Treatment approach: Immediate volume support and collagen stimulating treatments are priced differently. Collagen stimulating treatments may involve a series of sessions, which affects how the total cost is structured over time.
- Provider qualifications and clinic type: Doctor-led clinics with specialist training in facial anatomy typically sit at the higher end of the pricing range. Treatments performed by less experienced practitioners at lower-cost clinics carry a different risk profile that should be factored into any cost comparison.
- Location: Clinic costs vary between cities and between inner-city and suburban locations across Australia.
Smile lines treatment cost in Australia: typical ranges
| Treatment approach | Typical cost range (AUD) | Notes |
|---|---|---|
| Fold only — volume support | $1,500 – $1,800 | Targeted treatment of the nasolabial crease directly |
| Fold + midcheek volume support | $1,800 – $2,500 | Addresses upstream cause and the fold; typically a more complete result |
| Collagen stimulating treatment (per session) | $800 – $1,500 per session | Often requires 2–3 sessions; total investment higher but longevity greater |
| Combination approach | $2,000 – $2,500+ | Multiple treatment methods in the same appointment |
These ranges reflect pricing at established, doctor-led Australian clinics. Pricing at non-medical or nurse-led clinics may sit lower; the variation in training, anatomical knowledge, and complication management capability is worth understanding before making a decision on that basis alone.
Is smile lines treatment covered by Medicare or health insurance?
Non-surgical cosmetic treatment for nasolabial folds is not covered by Medicare or private health insurance in Australia. It is classified as a cosmetic procedure rather than a medical necessity. The full cost is payable by the patient.
Some clinics offer payment plan arrangements. At Cosmetic Connection, our payment options page outlines how appointments can be structured financially. It is worth asking about this at your consultation if it is relevant to your planning.
[ctaForm]
Flat-fee pricing vs variable pricing: why it matters
Pricing structures for cosmetic treatment vary significantly between clinics. Understanding the difference matters when comparing costs.
Variable pricing — sometimes called “per mL” or “per syringe” pricing — means the total cost of your appointment is not confirmed until the treatment is underway or complete. The price can increase during the session if more volume is used than initially estimated. This model can make it difficult to know your actual cost before committing.
Flat-fee pricing means the cost of your treatment is confirmed at consultation and does not change based on product quantities used during the procedure. At Cosmetic Connection, all treatments are priced on a flat-fee basis. You can view our complete treatment and pricing guide before booking, so there are no surprises.
Our guide to understanding cosmetic treatment pricing explains why the flat-fee model benefits patients and what to look for when comparing clinic pricing structures.
What should I expect to get for the cost?
When assessing value — rather than just cost — it helps to understand what a well-structured smile lines treatment appointment should include.
- A thorough face-to-face assessment of the fold, midface, and surrounding anatomy before any treatment is recommended
- A clearly explained treatment plan with realistic expected outcomes discussed before you commit
- Treatment performed or directly supervised by a doctor with specific training in facial anatomy
- A follow-up or review pathway if you have concerns after treatment
- Written aftercare instructions
In our experience, the most common source of patient dissatisfaction with smile lines treatment at other clinics is not the price paid — it is being treated without a thorough assessment, or being treated for an area that was not actually the primary driver of the concern. A slightly higher cost at a clinic that assesses suitability carefully is almost always better value than a lower cost at one that does not.
Is smile lines treatment worth the cost?
This depends entirely on how much the concern is affecting you day to day and what you are hoping treatment will achieve. It is a question worth being honest about at consultation.
Patients who tend to find the value strongest are those whose nasolabial folds are visible at rest, who consistently notice them in photos or mirrors, and who have realistic expectations about softening rather than eliminating the fold. The research supports meaningful, lasting improvement in these patients — a systematic review published in Aesthetic Plastic Surgery (Stefura et al., 2021) confirmed sustained improvement in fold severity scores through six months and gradual return toward baseline by 12 months, with most patients describing satisfying outcomes.
For patients who are only bothered by their smile lines when smiling, or whose folds are very mild, the cost-to-benefit ratio is less clear-cut — and an honest assessment may reflect that a different approach, or no treatment at the current time, is the more appropriate recommendation. This is exactly the kind of guidance our nasolabial fold treatment suitability guide covers in more detail.
[ctaForm]
Frequently asked questions
Why does smile lines treatment cost more at some clinics than others?
Pricing reflects the qualifications of the treating practitioner, the clinic’s overhead costs, the treatment model used, and whether pricing is flat-fee or variable. Doctor-led clinics with specialist training in facial anatomy typically sit at the higher end. The gap between the cheapest and most expensive options in Australia can be significant — and the difference in training, assessment quality, and complication management capability is a meaningful factor in that variation.
Does the cost of smile lines treatment include a consultation?
This varies between clinics. At Cosmetic Connection, the consultation and assessment are included as part of the appointment structure — you are not charged separately for the assessment conversation before treatment is confirmed. Check this with any clinic you are considering.
How often will I need to repeat treatment and what does that cost over time?
With volume support treatment, most patients return for maintenance at around 12 months. The cost per maintenance appointment is typically similar to the initial treatment. Collagen stimulating approaches involve a higher initial investment (often two to three sessions) but tend to extend the interval between treatments, which can reduce the annual cost over time.
Is cheaper smile lines treatment less safe?
Not necessarily — but lower-cost treatment often reflects a different level of practitioner training, anatomical knowledge, and assessment quality. The nasolabial fold is located in close proximity to vascular structures where complications, though rare, can be serious. Treatment performed by an experienced doctor with specialist facial anatomy training carries a different risk profile to treatment performed by a less experienced practitioner. This is worth considering when comparing options purely on price.
References
- Stefura T, Kacprzyk A, Droś J, Krzysztofik M, Skomarovska O, Fijałkowska M, Koziej M. (2021). Tissue Fillers for the Nasolabial Fold Area: A Systematic Review and Meta-Analysis of Randomized Clinical Trials. Aesthetic Plastic Surgery, 45(5), 2300–2316. https://doi.org/10.1007/s00266-021-02439-5
- Minelli L, Brown CP, Warren RJ, van der Lei B, Mendelson BC, Little JW. (2023). Lifting the Anterior Midcheek and Nasolabial Fold. Aesthetic Surgery Journal, 43(9), 941–954. https://doi.org/10.1093/asj/sjad126
Several non-surgical treatment options exist for nasolabial folds, and they work in meaningfully different ways. The right choice depends on what is causing your folds to deepen, how quickly you want to see results, how long you want them to last, and what your anatomy actually needs. This guide compares the main options side by side so you can go into your assessment with a clear picture of what each approach involves.
Quick answer: The two main non-surgical options for nasolabial folds are immediate volume support treatments and collagen stimulating treatments. Volume support produces visible results on the day and typically lasts 12 to 18 months. Collagen stimulating treatment builds gradually over several months and tends to last longer. For most patients presenting with moderate fold depth driven by midface volume loss, volume support — placed in the cheek, the fold, or both — is the most commonly recommended starting point.
Why the treatment choice depends on the cause
Before comparing treatment options, it helps to understand that nasolabial folds deepen for more than one reason — and not every approach addresses every cause equally well.
The three main drivers are: midface fat pad descent and volume loss (the most common cause); reduced bone support in the upper jaw, which causes overlying tissue to lose its foundation; and skin laxity, where the skin itself has thinned and lost the elasticity to remain supported. Most patients have a combination of all three in varying proportions.
This is why the same treatment approach does not produce the same outcome in every patient. A plan that works well for someone whose fold is primarily driven by midface volume loss may produce a modest result in someone whose fold is driven mainly by skin laxity. Accurate assessment — not a standard protocol — is what determines which option is most appropriate. You can read more about the structural causes of fold deepening in our complete guide to smile lines treatment.
Option 1: volume support treatment
Volume support treatment is the most commonly used non-surgical approach for nasolabial folds. It works by placing biocompatible material at a precise anatomical depth — either in the midcheek to restore structural lift, directly in the fold to address the crease, or both — to replace the volume the face has lost with age.
Results are visible immediately after treatment, with the final outcome apparent once any swelling has resolved — usually within one to two weeks. The effect typically lasts 12 to 18 months depending on the individual, the areas treated, and lifestyle factors.
A systematic review and meta-analysis published in Aesthetic Plastic Surgery (Stefura et al., 2021), which analysed randomised clinical trials of tissue volume treatments for the nasolabial fold area, found that average fold severity scores improved substantially from baseline at one month and remained meaningfully improved at six months, with gradual return toward baseline by 12 months. The evidence base for this approach is well-established across multiple high-quality trials.
Best suited for: Moderate to deep folds at rest; volume loss as the primary driver; patients who want visible results on the day.
Typical longevity: 12–18 months.
Downtime: 2–5 days of mild swelling and tenderness.
Option 2: collagen stimulating treatment
Collagen stimulating treatment works differently. Rather than placing volume directly, it triggers the body’s own collagen-building response over time. The result builds gradually over several months and tends to last significantly longer than immediate volume support approaches — in some cases 24 months or beyond.
The trade-off is timing. Patients who choose this approach should expect to wait two to four months before seeing meaningful change, and in some cases a series of treatment sessions is recommended to achieve the full result. It is not suitable for patients who want an immediate improvement.
A 2024 randomised controlled trial involving 260 participants reported a 67.6% improvement in wrinkle severity at 52 weeks using a poly-L-lactic acid collagen stimulating approach, with patient satisfaction exceeding 90%. A separate 2025 multicentre trial found this approach achieved strong midfacial volume correction at 12 months. The evidence base for collagen stimulating treatment is supported by Level 1 evidence across multiple randomised trials. Our collagen stimulating treatment page covers this approach in more detail.
Best suited for: Patients who prefer a gradual, longer-lasting approach; those with skin quality concerns alongside fold depth; patients happy to wait for results to build.
Typical longevity: 18–24+ months.
Downtime: Minimal. Some swelling in the first few days after each session.
[ctaForm]
Option 3: treating the cheek rather than the fold
This is not a separate treatment type — it is a strategic choice about where volume support is placed. Many patients assume treatment for nasolabial folds involves placing volume directly into the crease. In practice, treating the cheek and midface is often the more effective approach, because it addresses the upstream cause of fold deepening rather than the fold itself.
When volume is restored to the midcheek, it lifts the overlying tissue that has descended and effectively reduces the apparent depth of the fold without placing anything directly in the crease. The result tends to look more natural because it restores three-dimensional facial shape rather than simply filling a line.
Research published in Archives of Dermatological Research directly compared cheek volume restoration with alternative approaches for nasolabial fold improvement, finding statistically significant improvements in fold depth scores when cheek volume was addressed alongside nasolabial folds — supporting the clinical case for this upstream approach. Our guide to cheek volume treatment explains this in more detail.
Best suited for: Patients whose fold deepening is primarily driven by cheek descent and midface volume loss; those who want a more natural-looking result; patients already considering cheek treatment.
Option 4: combination approaches
In many cases, the most complete result comes from combining approaches rather than choosing one in isolation. A treatment plan might include midcheek volume support to restore structural lift alongside direct fold treatment to address any remaining crease depth — or a volume support approach in the short term with collagen stimulating treatment planned as the longer-term maintenance strategy.
Combination planning is assessed on an individual basis and depends on the patient’s anatomy, goals, and what the assessment finds. The holistic approach we use at Cosmetic Connection is built around treating the face as a whole system rather than addressing concerns in isolation. This tends to produce the most proportionate, natural-looking outcomes — particularly in the midface, where the nasolabial fold, cheeks, under-eyes, and lower face all interact with each other visually.
Side by side comparison
| Treatment option | How it works | Results visible | Longevity | Best for | Downtime |
|---|---|---|---|---|---|
| Volume support (fold direct) | Replaces volume in the crease | Immediately | 12–18 months | Deep resting folds; fold as primary concern | 2–5 days |
| Volume support (midcheek) | Lifts overlying tissue via upstream volume | Immediately | 12–18 months | Volume loss as primary driver; natural result priority | 2–5 days |
| Collagen stimulating treatment | Triggers body’s own collagen production | Gradually over 2–4 months | 18–24+ months | Longer-lasting result; skin quality concerns | Minimal |
| Combination approach | Multiple methods addressing different drivers | Partially immediate; builds over time | Varies | Complex presentations; comprehensive result | 2–5 days initially |
| Skincare only | Surface-level support; slows collagen loss | No | Ongoing maintenance required | Prevention | None |
What is not the right approach for nasolabial folds
It is worth being clear about what non-surgical treatment cannot address well, so expectations are accurate from the start.
Significant skin laxity — where the skin has substantially thinned and lost its attachment to underlying structures — is not well addressed by volume support alone. Adding volume in the presence of lax skin can sometimes make the area appear heavier rather than more lifted. In these cases, a surgical consultation may be a more appropriate referral. Similarly, very deep nasolabial folds present from a young age and driven primarily by facial structure rather than age-related volume loss may have limited response to volume support.
The assessment at Cosmetic Connection is specifically designed to identify these situations early — so you are not recommended a treatment that is unlikely to achieve what you are hoping for.
[ctaForm]
Frequently asked questions
Which nasolabial fold treatment option is best?
There is no single best option — the right approach depends on the cause of your fold deepening, your anatomy, and your goals. For most patients with moderate fold depth driven by midface volume loss, immediate volume support — placed in the cheek, the fold, or both — is the most effective starting point. For those who want longer-lasting results and are prepared to wait for them to build, collagen stimulating treatment is a strong alternative or complement.
Can I have nasolabial fold treatment and cheek treatment at the same time?
Yes, and in many cases this is the recommended approach. Treating the cheek and fold simultaneously addresses both the upstream cause of fold deepening and the crease itself, which tends to produce a more complete and natural-looking result than treating either area in isolation.
How do I know if I need volume in my cheeks or in the fold itself?
This is determined at assessment. If the fold looks deep primarily because the cheek above it has descended and lost volume, treating the cheek tends to produce a more natural result. If the fold itself is the primary concern and the cheek volume is relatively preserved, treating the fold directly may be more appropriate. In practice, many patients benefit from some volume in both areas.
Is collagen stimulating treatment painful?
Most patients find collagen stimulating treatment well-tolerated. A topical numbing preparation is used beforehand, and the procedure involves a series of small placements rather than a single site treatment. Some patients notice a mild tenderness in the treated area for a few days after each session.
What happens if I do not like the result of nasolabial fold treatment?
Volume support treatments using certain materials can be partially or fully dissolved if you are unhappy with the result or if a complication occurs. This is one of the key clinical safety advantages of this treatment approach. Collagen stimulating treatments cannot be reversed in the same way, though results fade naturally over time. Reversal options are discussed as part of every consultation.
References
- Stefura T, Kacprzyk A, Droś J, Krzysztofik M, Skomarovska O, Fijałkowska M, Koziej M. (2021). Tissue Fillers for the Nasolabial Fold Area: A Systematic Review and Meta-Analysis of Randomized Clinical Trials. Aesthetic Plastic Surgery, 45(5), 2300–2316. https://doi.org/10.1007/s00266-021-02439-5
- El-Mesidy MS, Alaklouk WT, Azzam OA. Nasolabial fold correction through cheek volume loss restoration versus thread lifting: a comparative study. Archives of Dermatological Research. 2020. https://doi.org/10.1007/s00403-019-02031-7
- Advances in Poly-l-lactic Acid Injections for Facial and Neck Rejuvenation. (2025). PMC / Journal of Cosmetic Dermatology. https://pmc.ncbi.nlm.nih.gov/articles/PMC12323926/